 Vascular Closure Device Vcd Market
Vascular Closure Device VCD Market Outlook 2026
Updated On : Nov 17, 2026|Base Year : 2025|Pages : 261

Amit Mardhekar
Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Vascular Closure Device Vcd Market
Amit Mardhekar
Research Analyst

| Year | Market Size |
|---|---|
| 2025 | 1.920 B |
| 2026 | 2.070 B |
| 2027 | 2.230 B |
| 2028 | 2.410 B |
| 2029 | 2.600 B |
| 2030 | 2.800 B |
| 2031 | 3.020 B |

The Vascular Closure Device VCD market covers single-use devices that seal arterial or venous puncture sites after catheterization, replacing manual compression. It spans active approximators, passive approximators, external hemostatic devices, and large-bore and venous systems used in cardiac, peripheral, and structural heart procedures.
This analysis covers global device revenue across active approximators, passive approximators, external hemostatic compression, and large-bore and venous closure systems used in cardiac, peripheral vascular, electrophysiology, and structural heart procedures. This analysis does not cover guidewires, sheaths, catheters, hemostasis pads sold as consumables outside the device class, or general surgical sealants.
Published estimates for the Vascular Closure Device VCD market diverge meaningfully — from roughly 1.85 Billion to 1.92 Billion for 2025 — with CAGRs spanning 5.4% to 7.9%. The gap reflects differing treatment of large-bore structural heart closure and ambulatory migration, not disagreement on procedure growth.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| 1.60 Billion | 2024 | 2030 | 5.7% | Active + passive approximators; excludes external compression | One published estimate |
| 1.85 Billion | 2025 | 2035 | 5.4% | All VCD types; conservative large-bore weighting | A competing analysis |
| 1.92 Billion | 2025 | 2035 | 7.85% | All VCD types including large-bore and venous; aggressive structural heart weighting | A third published analysis |
| 1.70 Billion | 2024 | — | — | Procurement-verified 2024 base | Trade consultation benchmark |
Our analysis suggests the higher-CAGR view is more defensible for the 2026-2035 window, because large-bore TAVR and venous closure were barely monetized in the 2024 base and are now scaling. The 5.4% view implicitly assumes large-bore pricing stays niche, which contradicts 100,501 U.S. TAVR procedures in 2023 and expanding ASC cardiac coverage from January 2025.
Segmentation matters because growth is not uniform: the fastest-moving tiers are large-bore closure, radial-specific compression, and venous multi-access closure, while routine passive femoral closure grows below market.
| Parent segment | Children |
|---|---|
| By Product | Active approximators (suture-mediated, clip-based), Passive approximators (collagen plug, sealant), External hemostatic devices, Large-bore closure devices, Venous closure devices |
| By Application | Cardiac interventions (PCI, TAVR, LAAC, EP), Peripheral vascular interventions, Cerebrovascular, Endovascular surgery |
| By Access Site | Femoral, Radial, Venous |
| By End-use | Hospitals and clinics, Ambulatory surgical centers, Catheterization laboratories |
Active approximators held 65.7% of 2024 revenue in one dataset and 54% in another — a definitional split over whether large-bore suture systems are counted inside active approximators. Our analysis suggests buyers should normalize this before comparing vendor shares.
North America leads the Vascular Closure Device VCD market with roughly 42% revenue share in 2025, anchored by more than 1.5 million annual U.S. cardiac catheterizations and the most favorable reimbursement climate globally. Asia Pacific is the fastest-growing region.
| Region | Market Share (%) |
|---|---|
| North America | 0.42% |
| Europe | 0.24% |
| Asia-Pacific | 0.24% |
| Latin America | 0.06% |
| Middle East & Africa | 0.04% |
| Region | 2025 share | Growth posture |
|---|---|---|
| North America | 42% | Largest, mid-single-digit growth |
| Europe | 24% | Stable, MDR-constrained entry |
| Asia Pacific | 24% | Fastest; China and Japan cath-lab expansion |
| Latin America | 6% | Emerging, price-sensitive |
| Middle East & Africa | 4% | Infrastructure-limited |
The U.S. alone was valued at roughly 0.55 Billion in 2025. Germany performs over 1,600 PCIs per million inhabitants annually, sustaining European volume even as radial-first adoption reshapes product mix toward compression platforms.
Growth is driven by structural heart procedure expansion, ASC reimbursement migration, and cardiovascular disease burden, while clinical confidence gaps and regulatory timelines constrain adoption speed rather than direction.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Structural heart and high-acuity cath volume | Driver | High | 100,501 U.S. TAVR procedures in 2023 raise large-bore closure demand |
| CMS ASC cardiac coverage from Jan 2025 | Driver | High | Outpatient migration creates routine closure demand in leaner settings |
| Global CVD burden | Driver | High | 19.8 million deaths in 2022 sustain catheterization infrastructure build-out |
| Vascular access complication rates | Restraint | High | 5.1% overall and 7.6% partial-deployment rates concentrate adoption in specialist centers |
| FDA PMA and EU MDR 2017/745 timelines | Restraint | Medium | Extended pre-market pathways delay new-entrant supply |
| Radial-first access shift | Restraint | Medium | Reduces femoral VCD demand per procedure |
The balance favors growth: drivers are volume-structural and reimbursement-anchored, while restraints are executional and therefore addressable through training and device design. Our analysis suggests the radial shift is a mix headwind, not a volume headwind — it redistributes value toward compression and radial-specific platforms rather than shrinking the category.
Abbott Vascular leads the Vascular Closure Device VCD market with roughly 32% share in 2025; the top five — Abbott, Terumo, Haemonetics, Cordis, and Teleflex — collectively hold roughly 74%, indicating a concentrated but not closed competitive field.
| Vendor | Position | Differentiation |
|---|---|---|
| Abbott Vascular | Leader, ~32% | Broad active approximator portfolio and deep cath-lab training footprint |
| Terumo | Top tier | Radial access heritage and global distribution |
| Haemonetics | Top tier | Venous closure via VASCADE MVP and MVP XL (10-15 Fr) |
| Cordis | Top tier | MYNX CONTROL venous and femoral platforms |
| Teleflex | Top tier | MANTA large-bore closure for 14-25 Fr structural heart access |
Differentiation is shifting from deployment speed to sheath compatibility breadth and operator training depth. Moats are built on clinical evidence and installed-base familiarity — the AMBULATE trial's 54% reduction in time to ambulation for VASCADE MVP is the template for commercial advantage. Smaller entrants face PMA evidence cost as a structural barrier.
Procurement decisions should be anchored on four criteria: complete-closure reliability across operator skill levels, sheath-size coverage for structural heart programs, venous multi-access capability for EP workflows, and supplier training infrastructure. Partial deployment carries disproportionate cost — re-intervention, delayed discharge, and institutional scrutiny.
Switching costs are underappreciated. Once a closure protocol is embedded in cath-lab workflow and physician training, conversion requires parallel evidence generation and formulary re-approval, often a 12-24 month cycle. Buyers should therefore negotiate training and post-market evidence commitments, not just unit price.
Regulatory compliance is a gating factor: FDA PMA and EU MDR 2017/745 demand controlled clinical evidence for novel closure architectures. Single-source risk is real in large-bore closure, where viable platforms remain few — buyers should qualify at least two suppliers per sheath-size tier.
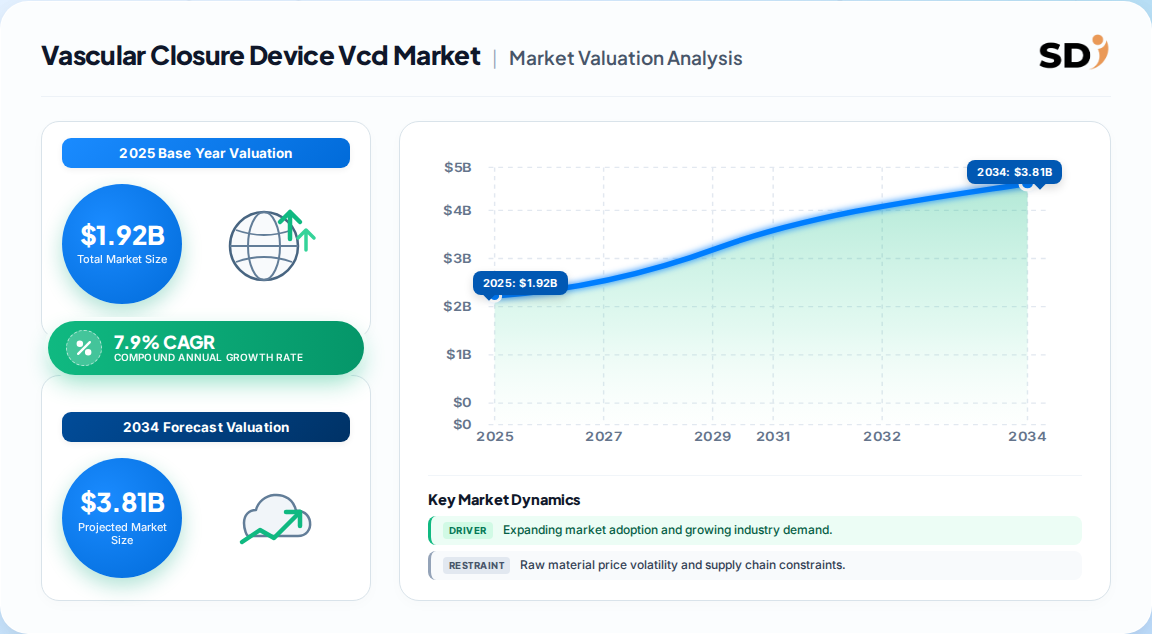
The balance of evidence favors the higher-growth outlook: a 7.9% trajectory to 2035, driven by large-bore structural heart closure and ASC migration rather than by routine femoral volume. The strongest counter-argument is that radial-first adoption and complication-driven consolidation could suppress per-procedure VCD value in lower-acuity settings, compressing blended pricing even as unit volumes rise.
Our analysis suggests the market's value is bifurcating. Routine small-bore femoral closure is becoming commoditized and price-sensitive; large-bore and venous closure remain premium and evidence-gated. Vendors positioned only in the commoditizing tier should expect margin compression by 2030, while those with structural-heart and venous platforms can defend pricing.
What would change our conclusion: a sharp drop in TAVR and LAAC procedural growth, or a step-change in complication rates for large-bore devices, would compress the premium tier and invalidate the 7.9% view. Precise sub-segment forecasting by sheath size and access site requires the full report's granular model.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 7.9% from 2020-2034 |
| Segmentation |
|
The global Vascular Closure Device VCD market was valued at roughly 1.9 Billion in 2025 and is projected to reach about 4.1 Billion by 2035 at a 7.9% CAGR, driven by structural heart procedure growth and ambulatory cardiac migration.
Active approximators are the largest product segment, holding roughly 54-66% of revenue depending on whether large-bore suture systems are counted inside that tier. Large-bore closure devices are the fastest-growing sub-segment on TAVR and LAAC volumes.
Abbott Vascular leads with roughly 32% share. Terumo, Haemonetics, Cordis, and Teleflex complete the top five, which together hold approximately 74% of global revenue, leaving a concentrated but contestable competitive field.
Asia Pacific grows fastest because catheterization laboratory infrastructure is expanding in China, Japan, and India, and China's NMPA accepted 61 innovative device dossiers in 2023, accelerating local and imported device availability in price-sensitive but high-volume markets.
Complication risk and regulatory timelines restrain adoption. Vascular access complication rates reach 5.1%, and partial deployment rates reach 7.6%, concentrating device use in specialist centers and lengthening conversion cycles for newer platforms under FDA PMA and EU MDR pathways.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our research employs a 70/30 primary-to-secondary split. In-depth interviews were conducted across the value chain with raw material and biomaterial suppliers, specialized VCD manufacturers, contract manufacturing and sterilization partners, and global distributors. Within these organizations we engaged decision-makers including VP-level Sourcing leads, Heads of R&D and Device Engineering, Technical and Clinical Directors, and Commercial Operations Leads responsible for cath-lab procurement.
| Stakeholder Role | Interview Share (%) |
|---|---|
| R&D & Device Engineering Heads | 35% |
| Procurement & Sourcing Directors | 30% |
| Clinical & Regulatory Affairs Leads | 20% |
| Commercial Operations Leads | 15% |
| Company Type | Representation (%) |
|---|---|
| VCD Manufacturers & OEMs | 40% |
| Biomaterial & Component Suppliers | 25% |
| Global Distributors | 20% |
| Hospitals & Cath-Lab Operators | 15% |
We validate primary findings against official multilateral and regulatory sources, including UN Comtrade and US ITC trade flows, Eurostat medical device statistics, WTO tariff schedules, corporate SEC 10-K filings and investor presentations, patent databases, and recognized standards bodies including ISO 13485 and ISO 10993 biocompatibility frameworks. No competitor market research publications are used as validation inputs.
Market sizing uses simultaneous top-down and bottom-up triangulation. Top-down, we allocate macroeconomic healthcare expenditure and interventional procedure volumes by region. Bottom-up, we model manufacturer capacity, average selling prices by sheath-size tier, and end-use consumption across hospitals, ASCs, and catheterization laboratories, reconciling both views to a single base-year value.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |