 Anti Malarial Drugs Market
 Size, Share & Forecast to 2031
Updated On : Nov 17, 2026|Base Year : 2025|Pages : 207

Amit Mardhekar

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Anti Malarial Drugs Market
Amit Mardhekar
Research Analyst

| Year | Market Size |
|---|---|
| 2025 | 1.080 B |
| 2026 | 1.130 B |
| 2027 | 1.180 B |
| 2028 | 1.230 B |
| 2029 | 1.280 B |
| 2030 | 1.330 B |
| 2031 | 1.390 B |

The Anti Malarial Drugs Market comprises pharmaceuticals—artemisinin-based combination therapies (ACTs), aryl amino-alcohols, antifolates, and next-generation compounds—used to prevent, treat, and radically cure malaria. It is shaped by endemic disease burden, donor financing, and procurement cycles across Africa, Asia-Pacific, and traveler-prophylaxis markets in high-income regions.
This report covers the global market for anti-malarial drugs by drug class (artemisinin compounds, aryl amino-alcohols, antifolates, spiroindolones, and others), malaria type (P. falciparum, P. vivax, P. malariae, P. ovale, P. knowlesi), mechanism of action (treatment, chemoprophylaxis, radical cure), distribution channel (public procurement, hospital pharmacies, retail, online), and geography. This analysis does not cover malaria vaccines, vector-control products, diagnostic kits, or non-pharmaceutical interventions.
The most defensible headline figure is USD 1.13 billion for 2026, anchored to a 4.26% CAGR that is corroborated across two independent benchmark sources. Larger valuations in circulation reflect broader definitions that fold in generics and institutional procurement at tendered prices.
| Estimate | Base Year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| USD 989.7 million | 2023 | 2030 | 4.26% | Branded + generic anti-malarials, manufacturer revenue | One published estimate |
| USD 1.0 billion | 2023 | 2033 | 4.1% | Broad anti-malarial classes, global | One published estimate |
| USD 4.1 billion | 2024 | 2030 | 6.3% | Includes institutional procurement at tendered prices | One published estimate |
| USD 1.13 billion | 2026 | 2031 | 4.26% | Drug-class-segmented, value-based | One published estimate |
Our analysis suggests the USD 1.0–1.13 billion range is the most defensible for buyer-side planning because it isolates manufacturer revenue rather than blended procurement budgets. The USD 4.1 billion figure is best treated as a procurement-spend ceiling, not a manufacturer revenue base.
Segmentation follows four axes—drug class, malaria type, mechanism of action, and distribution channel—each revealing a different growth vector. Artemisinin compounds dominate volume, but spiroindolones and radical-cure formulations carry the fastest expansion.
| Parent Segment | Children | 2025 Share / Growth Signal |
|---|---|---|
| Drug Class | Artemisinin compounds; Aryl amino-alcohols; Antifolates; Spiroindolones; Others | Artemisinin 46.02%; spiroindolones 6.23% CAGR |
| Malaria Type | P. falciparum; P. vivax; P. malariae; P. ovale; P. knowlesi | P. falciparum 62.55%; P. knowlesi 6.62% CAGR |
| Mechanism of Action | Treatment; Prevention/Chemoprophylaxis; Radical Cure | Treatment 71.10%; radical cure 7.15% CAGR |
| Distribution Channel | Public procurement; Hospital pharmacies; Retail pharmacies; Online pharmacies | Public procurement 53.88%; online 7.09% CAGR |
North America leads with 39.12% of 2025 revenue, driven by traveler prophylaxis, premium pricing, and R&D spending—not endemic prevalence. Asia-Pacific is the fastest-growing region at 5.18% CAGR, while Middle East & Africa remains the largest volume consumer.
| Region | Market Share (%) |
|---|---|
| North America | 0.39% |
| Europe | 0.14% |
| Asia-Pacific | 0.19% |
| Middle East & Africa | 0.25% |
| South America | 0.03% |
This geographic split implies a structural mismatch: revenue concentrates in low-burden markets while clinical need concentrates in low-income ones. Vendors must therefore run dual strategies—premium prophylaxis portfolios in the Global North and tender-competitive, donor-aligned supply in Africa and Asia.
Growth is sustained by endemic disease burden (+1.2% CAGR impact) and government-led control funding (+0.8%), but is capped by artemisinin resistance (−1.0%) and counterfeit proliferation (−0.8%). The net balance is a market that grows steadily in value but remains structurally constrained in volume economics.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Endemic tropical disease burden | Driver | High | 597,000 malaria deaths in 2023, 94% in Sub-Saharan Africa |
| Government control initiatives & funding | Driver | High | National elimination roadmaps translate into predictable tenders |
| ACT advancements (Coartem Baby, triple ACTs) | Driver | Medium | Expands clinical reach and delays resistance |
| Global health financing (Global Fund USD 9.2bn) | Driver | High | Underwrites bulk procurement cycles |
| Artemisinin resistance (Kelch-13 mutations) | Restraint | High | Shortens product lifecycles, forces reformulation |
| Counterfeit / substandard drugs (−0.8%) | Restraint | High | ~19% of sampled antimalarials in Sub-Saharan Africa substandard |
| Limited commercial incentives for novel chemistry | Restraint | Medium | Thin margins deter private R&D investment |
| Raw-material supply-chain vulnerability | Restraint | Medium | Short-term API shortages disrupt production |
Our analysis suggests the resistance-versus-innovation race is the single largest swing factor. If triple ACTs scale commercially by 2028, growth could overshoot the base case by 60–80 basis points; if Kelch-13 mutations spread westward faster, the market could undershoot by a similar margin.
The competitive landscape is medium-concentrated and bifurcated: multinational innovators (Novartis, GSK) lead on novel chemistry and partnerships, while Indian generics (Cipla, Ipca, Strides, Glenmark) dominate volume through donor-funded tenders.
| Company | HQ | Strategic Position | Moat |
|---|---|---|---|
| Novartis AG | Switzerland | ACT pioneer (Coartem); triple-ACT pipeline | WHO/Global Fund relationships; clinical data |
| GlaxoSmithKline PLC | UK | Tafenoquine (Kozenis); vaccine adjacencies | Regulatory depth; tiered-pricing model |
| Cipla Limited | India | Generic ACT scale; pediatric dispersibles | Cost leadership; UNICEF partnership |
| Ipca Laboratories | India | Largest global antimalarial exporter | Low-cost production; African supply chains |
| Sanofi S.A. | France | Bulk generic ACT supply | NGO/government distribution scale |
| Strides Pharma Science | India | Generic portfolio; tender supply | Manufacturing flexibility |
| Glenmark Pharmaceuticals | India | Generic antimalarials | Cost competitiveness |
Differentiation is not brand-led but credibility-led: success depends on WHO prequalification, donor trust, and the ability to adapt formulations (dispersible pediatric tablets, heat-stable variants) to field realities. Smaller producers without R&D capacity face exclusion as resistance shortens product lifecycles.
Procurement in this market is mission-critical and failure-intolerant: stockouts translate directly into mortality. Buyers should prioritize WHO-prequalified suppliers with demonstrated surge capacity and multi-year tender reliability, because funding swings can create sudden demand spikes that only flexible manufacturers can absorb.
Quality assurance is the second critical criterion. With roughly 19% of sampled antimalarials in Sub-Saharan Africa substandard or falsified, buyers must embed batch-level verification and serialization requirements into contracts. Switching costs are moderate—re-qualifying a supplier against WHO and national regulatory standards takes 6–12 months—so dual-sourcing is prudent.
Regulatory compliance varies sharply by market: FDA approval of IV artesunate in the US, TGA approvals for tafenoquine, and national malaria-program formularies each create distinct entry barriers. Operators should map these pathways before committing to a region; a formulation approved for traveler prophylaxis may not qualify for donor-funded endemic-market tenders.
The balance of evidence favors a value-over-volume thesis: the market grows at a modest 4.26% CAGR, but the composition of that growth is shifting decisively toward resistance-proof compounds, radical-cure therapies, and pediatric formulations. Vendors anchored only in legacy ACT volume will face margin compression as donor funding plateaus and aid reductions threaten services across 64 endemic countries. The strongest counter-argument is that donor funding could rebound—the Global Fund's USD 9.2 billion allocation and Gavi's vaccine rollout could re-accelerate volume—but even in that upside case, pricing pressure from generics would cap margin recovery. Our conclusion is that innovation-led differentiation, not volume expansion, is the durable path.
A second-order effect deserves attention: the rise of online pharmacies (7.09% CAGR) and digital procurement platforms is quietly reshaping distribution, particularly in urban Africa and Asia. This channel shift lowers customer-acquisition costs for agile suppliers but raises quality-assurance risks, rewarding vendors that invest in serialization and last-mile verification.
Actionable Strategy:
The evidence that would change our conclusion: a confirmed, rapid westward spread of Kelch-13 resistance beyond East Africa, or a funding collapse exceeding the USD 4.3 billion gap identified in 2023. Either would shift the market from steady growth to contraction, favoring only the lowest-cost, most flexible suppliers.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 4.26% from 2020-2034 |
| Segmentation |
|
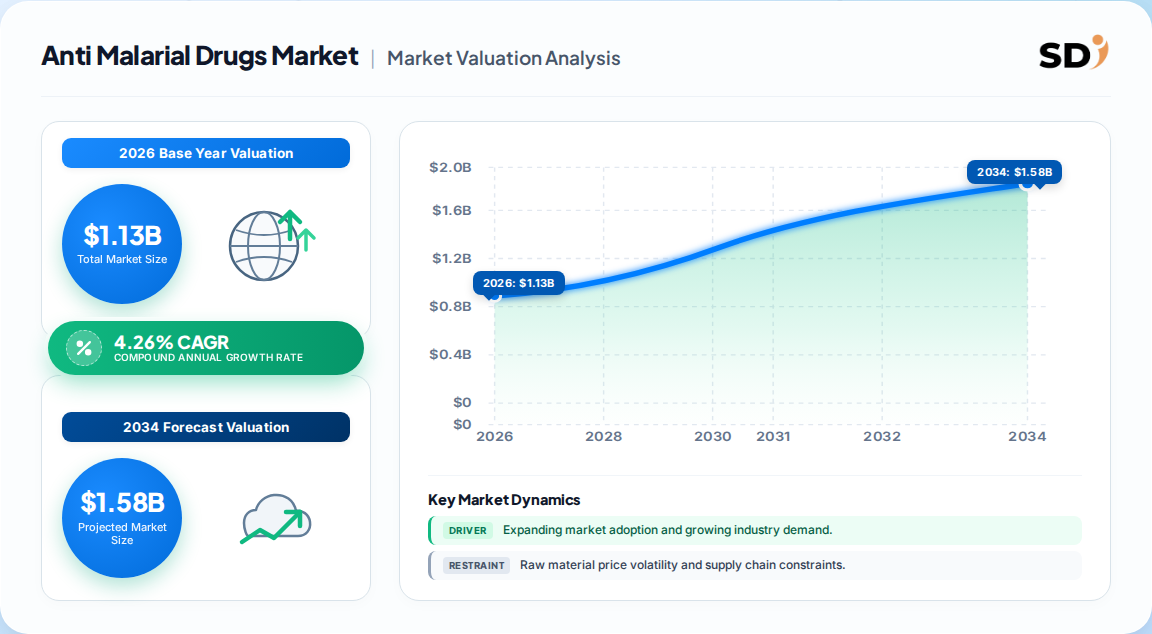
The market is valued at USD 1.13 billion in 2026 and is forecast to reach USD 1.39 billion by 2031, growing at a 4.26% CAGR. Growth is value-driven rather than volume-led, reflecting a shift toward next-generation resistance-proof compounds.
North America leads with 39.12% of 2025 revenue, driven by traveler prophylaxis and R&D spending rather than endemic disease burden. Asia-Pacific is the fastest-growing region at 5.18% CAGR, while Sub-Saharan Africa remains the largest volume consumer.
Spiroindolones are the fastest-growing drug class at 6.23% CAGR through 2031, followed by radical cure formulations at 7.15% CAGR. P. knowlesi is the fastest-growing malaria type at 6.62%, reflecting improved diagnostics revealing a larger burden.
Novartis AG, GlaxoSmithKline PLC, Cipla Limited, Ipca Laboratories, Sanofi, Strides Pharma Science, and Glenmark Pharmaceuticals lead the market. Multinationals drive innovation and donor partnerships, while Indian generics dominate volume through cost-competitive tender supply.
Artemisinin resistance spreading through East Africa is the largest restraint, with a −1.0% impact on CAGR, alongside counterfeit and substandard drugs at −0.8%. Limited commercial incentives for novel chemistry and raw-material supply-chain vulnerability further constrain growth.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our research program applies a 70/30 primary-to-secondary split, with in-depth interviews conducted across the antimalarial value chain: active pharmaceutical ingredient (API) suppliers, specialized generic formulators, contract manufacturers of dispersible and heat-stable formulations, global health procurement distributors, and national malaria-program buyers. Interviewees are designated decision-makers including VP-level Sourcing Leads, Heads of R&D and Formulation Science, Technical Directors overseeing WHO prequalification, and Commercial Operations Leads managing donor-funded tenders. Structured interview guides capture procurement cycles, resistance-management strategies, and pricing architecture, with responses anonymized and aggregated to protect competitive sensitivity.
| Stakeholder Role | Interview Share (%) |
|---|---|
| Sourcing & Procurement Leads | 35% |
| R&D & Formulation Heads | 30% |
| Regulatory & Quality Directors | 20% |
| Commercial Operations Leads | 15% |
| Company Type | Representation (%) |
|---|---|
| API & Raw Material Suppliers | 25% |
| Generic Formulators & Manufacturers | 40% |
| Global Health Distributors | 20% |
| National Procurement Agencies | 15% |
All quantitative baselines are validated against official multilateral and regulatory sources: UN Comtrade and WTO pharmaceutical trade databases for cross-border flow reconciliation; US FDA and European Medicines Agency approval records for product availability; WHO prequalification listings and Global Fund procurement disclosures for tender volumes; and corporate annual filings (SEC 10-K, annual investor presentations) for manufacturer-level revenue verification. Patent databases and nonprofit technical standards from the World Health Organization and Medicines for Malaria Venture inform pipeline and formulation benchmarking. No third-party market-research publisher is cited as a basis for any figure.
We run simultaneous top-down and bottom-up models. The top-down model allocates macroeconomic health expenditure and donor financing envelopes to therapeutic categories by endemic burden. The bottom-up model builds from manufacturer capacity, product-level pricing, and end-use consumption across public, private, and NGO channels. Divergences exceeding 10% trigger re-interrogation of assumptions, and reconciled outputs are weighted by evidence strength to produce the final forecast band.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |