 Healthcare Education Market
 Size, Growth & Forecast 2026-2031
Updated On : Nov 18, 2026|Base Year : 2025|Pages : 264

Amit Mardhekar
Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Healthcare Education Market
Amit Mardhekar
Research Analyst

| Year | Market Size |
|---|---|
| 2026 | 156.6 B |
| 2027 | 168.0 B |
| 2028 | 180.3 B |
| 2029 | 193.5 B |
| 2030 | 207.6 B |
| 2031 | 222.7 B |

The healthcare education market is the commercial ecosystem delivering undergraduate, postgraduate, continuing, and point-of-care clinical training — spanning digital platforms, simulation hardware, courseware, and CME providers. It serves medical schools, hospitals, nursing programs, and practicing clinicians, and is sized at roughly USD 156.6 billion in 2026 by one published estimate.
This analysis covers academic medical and nursing education, continuing medical education (CME), hospital-based workforce training, digital learning platforms, clinical simulation, and assessment tooling across inpatient and outpatient care settings globally. It segments by delivery mode, medical field, end user, and provider type.
This analysis does not cover pharmaceutical clinical-trial training, medical-device service contracts, general K-12 health literacy programs, or consumer wellness content — adjacent categories that appear in some vendor portfolios but follow distinct procurement economics.
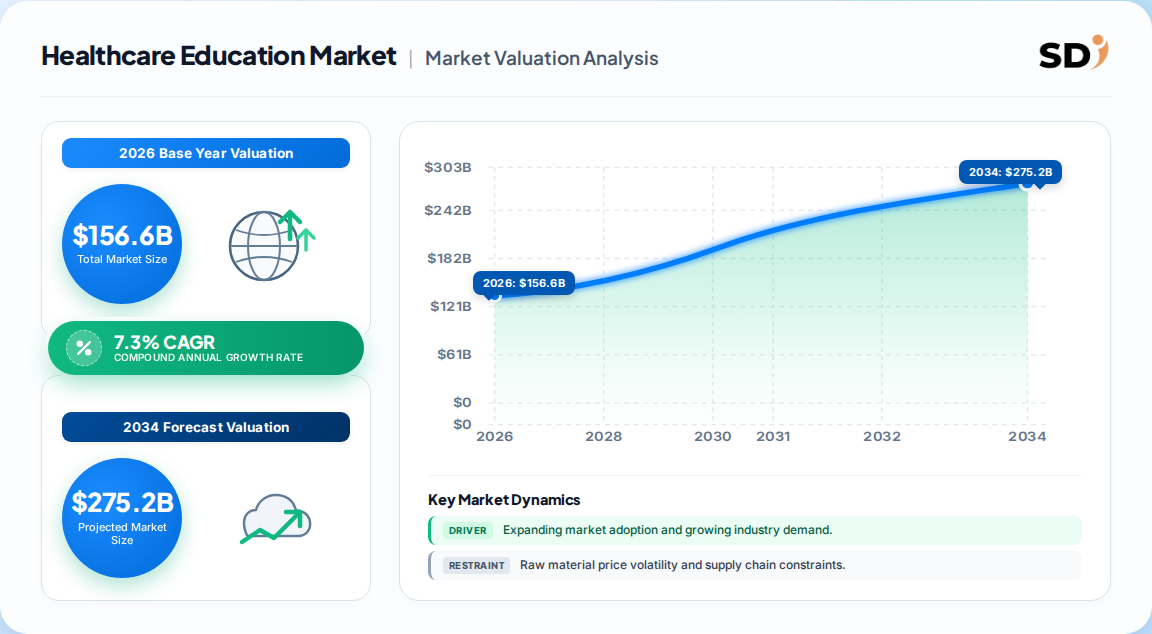
Estimates diverge sharply because publishers define the boundary differently: some count only digital platforms and courseware, others include university tuition-linked revenue and simulation hardware. The most defensible all-in figure for 2026 is approximately USD 156.6 billion, consistent with a 7.3% CAGR to 2031.
| Estimate (base year) | 2026 / Base Value | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| All-in healthcare education | USD 156.6B (2026) | 2031 | 7.3% | Academic + CME + hospital training + simulation | One published forecast |
| Medical education (narrower) | USD 123.47B (2025) | 2035 | 8.37% | Medical/nursing/dental/pharma curricula, mostly academic | A competing analysis |
| Healthcare education (2023 base) | USD 108.6B (2023) | 2033 | 8.56% | Universities, platforms, simulation, consumer health | A competing analysis |
| Healthcare education solutions | USD 11.13B (2026) | 2031 | 10.73% | Software platforms, courseware, services only | A competing analysis |
Our analysis suggests the USD 156.6B figure is most defensible for enterprise buyers because it reconciles platform spend with the substantial university and CME-provider budgets that pure-software estimates omit. The USD 11.13B "solutions" figure is best read as the addressable software-and-services slice, not the total market.
Segmentation matters because growth rates differ by 3–5 percentage points across delivery modes and end users, so blended averages obscure where budget is actually shifting. The table below reflects the consensus structure across reference estimates.
| Parent segment | Children | 2026 share / growth signal |
|---|---|---|
| Delivery mode | Classroom-based, E-learning, Blended, Simulation-based | E-learning ~64% of value; simulation CAGR ~12% |
| Medical field | Internal medicine, Cardiology, Neurology, Radiology, Pediatrics, Others | Internal medicine ~24% of value |
| End user | Students, Physicians, Non-physicians | Physicians ~40%; non-physicians ~9.0% CAGR |
| Provider type | Universities, Educational platforms, LMS, CME providers, OEMs/pharma, Medical simulation | Universities largest (~37.8%); simulation fastest |
| Technology | LMS, VR/AR, AI/ML, Digital twin, Assessment platforms | LMS ~53% of solutions spend |
E-learning dominates because it scales across multi-site health systems, but simulation-based training carries the pricing power: it cannot be substituted with content and requires hardware, scenarios, and faculty debriefing. Buyers should treat the 64% e-learning share as a floor, not a ceiling.
North America leads with approximately 39% of global healthcare education value in 2026, driven by mature CME compliance frameworks, the largest academic medicine ecosystem, and high hospital training budgets. Asia-Pacific is the fastest-growing region, anchored by India's 18.1% CAGR and China's expanding medical-school pipeline.
| Region | Market Share (%) |
|---|---|
| North America | 0.39% |
| Europe | 0.27% |
| Asia-Pacific | 0.24% |
| Latin America | 0.06% |
| Middle East & Africa | 0.04% |
| Region | 2026 share |
|---|---|
| North America | 39% |
| Europe | 27% |
| Asia-Pacific | 24% |
| Latin America | 6% |
| Middle East & Africa | 4% |
The Asia-Pacific trajectory implies a structural shift in vendor economics: content localized for Indian and Chinese curricula and languages will command premium pricing within 3–4 years. Our analysis suggests vendors without APAC localization will cede the fastest-growing pool of new learners.
Growth is driven by a structural clinical workforce shortage — WHO projects an 11 million worker shortfall by 2030 — combined with expanding CME mandates and hospital digitization that embeds training into clinical workflow. Restraints are real but secondary: rural adoption gaps, budget cyclicality, and faculty resistance to platform change.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Clinical faculty shortages | Driver | High (+2.8% CAGR impact) | E-learning lets small faculty pools supervise larger cohorts |
| Government-mandated CME | Driver | High (+2.1%) | Automated credit tracking and multi-jurisdiction reporting |
| Hospital workflow digitization | Driver | Medium (+1.9%) | Micro-learning embedded in EHR and decision-support screens |
| AR/VR simulation uptake | Driver | Medium (+1.7%) | Risk-free rehearsal for high-acuity procedures |
| Rural adoption resistance | Restraint | Medium | Low engagement slows institutional program launch |
| Budget cyclicality | Restraint | Medium | Capital-intensive simulation purchases deferrable |
The balance clearly favors growth. The binding constraint is not demand but institutional absorptive capacity — schools and hospitals lack the integration staff to deploy platforms they have already budgeted for. This implies services revenue (integration, content customization, analytics) will outgrow software licenses, consistent with services posting the highest solutions-segment CAGR at 11.31%.
The competitive field splits into content incumbents (Elsevier, Wolters Kluwer, McGraw Hill, Pearson), clinical-technology vendors (GE HealthCare, Siemens Healthineers, Medtronic, Stryker, FUJIFILM), and platform/simulation specialists (HealthStream, Laerdal, Symplr, Coursera). No single player exceeds mid-teens share, confirming a fragmented, medium-concentration market.
| Company | Core strength | Strategic moat | Watch item |
|---|---|---|---|
| Elsevier | Osmosis, ClinicalKey Student, Sherpath AI | Content library + 450+ medical-school relationships | AI monetization pace |
| Wolters Kluwer | Lippincott CoursePoint+, IntelliLearn acquisition | Nursing courseware depth + workflow integration | Post-acquisition integration |
| GE HealthCare | HelloAI, device-linked training | Installed-base lock-in on imaging equipment | AI curriculum as recurring revenue |
| Laerdal | SimMan, simulation ecosystems | Hardware + scenarios + debriefing bundle | VR substitution risk |
| HealthStream | 20,000+ course library, Red Cross certifications | Workforce compliance and credentialing | Content commoditization |
| McGraw Hill | Clinical Reasoning AI, Navigator (38 specialties) | Curriculum mapping and competency frameworks | Specialty coverage depth |
Differentiation is shifting from content breadth to assessed outcomes. Vendors that can evidence competency improvement — not just course completion — will win hospital procurement, because value-based reimbursement now links training spend to quality metrics. Our analysis suggests the moat is the assessment layer, not the library.
Selection criteria have consolidated around four tests: accreditation coverage across jurisdictions, integration with EHR and LMS environments, measurable competency analytics, and total cost including content refresh. Buyers who weight only license price consistently underestimate the 3–5 year cost of content localization and faculty retraining.
Procurement risk is concentrated in switching costs. Once CME credit tracking and competency records live in a platform, migration means re-validating accreditation history — a multi-quarter, compliance-sensitive process. Operators should negotiate data-portability and credit-history export clauses at signing, not at renewal.
Regulatory compliance is the sharpest differentiator. US DEA substance-use-disorder training requirements, state-board hour mandates (25–50 annually by jurisdiction), and WFME competency-based standards all demand granular activity-to-skill mapping. Platforms without this mapping fail hospital audits, regardless of content quality.
Finally, buyers should stress-test AI features for clinical accuracy governance. Generative study tools without evidence-traceability introduce liability in CME contexts; require vendors to document source attribution and human-review workflows before scaling deployment.
The balance of evidence favors a "services-led platform" thesis: the healthcare education market grows at a solid 7.3%, but value is migrating from content licenses toward integration, assessment, and compliance automation. The strongest counter-argument is that AI could commoditize content fast enough to compress platform pricing before services scale — a real risk for undifferentiated courseware vendors, but not for those owning accreditation workflows.
Second-order effects matter more than headline CAGR. Workforce shortages force larger cohort sizes, which force asynchronous and simulation delivery, which in turn raises demand for assessment integrity — a chain that favors vendors with competency analytics. Similarly, AI adoption in clinical practice (AMA data shows physician AI use at 81%) creates a recurring new CME subject area, giving incumbents a renewable content franchise.
Geographically, the divergence between North America's 39% share and Asia-Pacific's growth rate is the central strategic tension. Our analysis suggests the winning posture is to defend North American compliance revenue while deploying localized, lower-cost content in India and China before local champions consolidate.
Evidence that would change this conclusion: a sharp consolidation of CME accreditation into a single global standard, or AI regulation that certifies general-purpose models for clinical education — either would erode the compliance moat that underpins current vendor margins.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 7.3% from 2020-2034 |
| Segmentation |
|
The global healthcare education market is valued at approximately USD 156.6 billion in 2026, according to one published estimate. It is projected to reach USD 222.7 billion by 2031, growing at a 7.3% compound annual growth rate over the forecast period.
The market is forecast to grow at a 7.3% CAGR from 2026 to 2031. Faster-growing sub-segments include simulation-based training at roughly 12% and non-physician education at approximately 9.0% annually, outpacing the blended market average.
North America leads with approximately 39% of global market value in 2026, supported by mature CME frameworks and large academic medicine budgets. Asia-Pacific is the fastest-growing region, with India forecast to expand at an 18.1% CAGR through 2033.
Leading players include Elsevier, Wolters Kluwer, McGraw Hill, Pearson, GE HealthCare, Siemens Healthineers, Laerdal, HealthStream, and Coursera. The market is fragmented with medium concentration, and no single vendor holds a dominant share across all segments.
E-learning accounts for roughly 64% of global healthcare education value in 2026 because it scales across multi-site health systems and compensates for clinical faculty shortages. It lets small instructor pools supervise larger cohorts without compromising accreditation standards.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our research program applies a 70/30 primary-to-secondary split, with structured interviews forming the evidentiary core. We conducted in-depth interviews with stakeholders across the healthcare education value chain: content and courseware publishers, learning-platform and LMS providers, clinical simulation manufacturers, CME accreditation bodies, and hospital education departments. Within these organizations we targeted decision-makers including Chief Learning Officers, VP-Level Academic Affairs leads, Nursing Education Directors, and Procurement Heads for clinical training.
| Stakeholder Role | Interview Share (%) |
|---|---|
| Chief Learning & Academic Affairs Officers | 35% |
| Nursing & Clinical Education Directors | 30% |
| Procurement & Sourcing Heads | 20% |
| Compliance & Accreditation Leads | 15% |
| Company Type | Representation (%) |
|---|---|
| Content & Courseware Publishers | 35% |
| Learning Platform & LMS Providers | 30% |
| Clinical Simulation Manufacturers | 20% |
| Hospitals & Academic Institutions | 15% |
Secondary validation draws on official multilateral and national databases — UN Comtrade, WTO services trade statistics, USITC DataWeb, Eurostat, and OECD trade-by-enterprise-characteristics datasets — alongside corporate annual filings (10-K, SEC submissions), investor presentations, patent filings, and standards published by accrediting and professional bodies. No third-party market-research publisher is used as a validation source.
We run simultaneous top-down and bottom-up models. The top-down path allocates macroeconomic health-spending and education budgets across segments; the bottom-up path models institutional training budgets, platform seat pricing, simulation unit economics, and end-user consumption. Divergence between the two is reconciled at the segment level before any forecast is published.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up budget & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Trade flow analysis & institutional budget mapping | High |
| Competitive Landscape | Leading market players | Annual reports, platform mapping & commercial filings | High |