 Hospital Services Market
 Size, Growth & 2030 Outlook
Updated On : Nov 17, 2026|Base Year : 2025|Pages : 203

Amit Mardhekar

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Hospital Services Market
Amit Mardhekar
Research Analyst

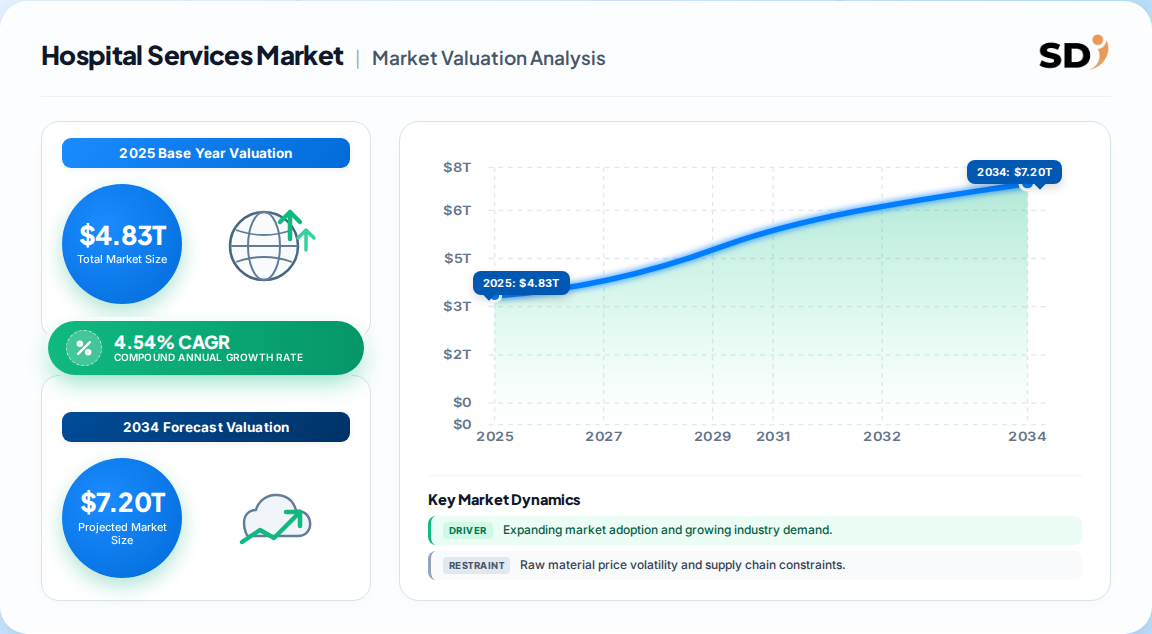
| Year | Market Size |
|---|---|
| 2025 | 4.830 M |
| 2026 | 5.050 M |
| 2027 | 5.280 M |
| 2028 | 5.520 M |
| 2029 | 5.770 M |
| 2030 | 6.030 M |

The hospital services market encompasses inpatient, outpatient, emergency, and ancillary clinical services delivered by public, non-profit, and for-profit hospitals. It covers acute care, surgical procedures, diagnostics and imaging, cancer and cardiovascular care, rehabilitation, and psychiatry, priced through negotiated tariffs, insurance reimbursement, and out-of-pocket payment across public and private payers.
This analysis covers the global delivery of hospital-based clinical services across all ownership models, service types, hospital sizes, and payer categories, spanning inpatient and outpatient care, emergency services, diagnostics, and specialised therapeutic areas. It excludes standalone pharmaceutical manufacturing, medical-device production, outpatient clinic-only providers, long-term care facilities, and health insurance underwriting.
Published estimates converge on a multi-trillion-dollar market, but the spread between them is wide enough to matter for investment cases. The table below normalises the leading figures against their stated base years and definitions.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| USD 4.2 Trillion | 2023 | 2030 (USD 5.7T) | 4.3% | Global hospital services, in+outpatient | One published estimate |
| USD 4.83 Trillion | 2025 | 2030 (USD 6.03T) | 4.54% | Global, all ownership and payer types | A competing analysis |
| USD 3.23 Trillion | 2024 | 2035 (USD 8.0T) | 8.6% | US-only hospital services | A third published estimate |
| USD 8.8 Trillion | 2020 | 2030 (USD 15.8T) | 9.1% | Broad health-services definition | A legacy published estimate |
Our analysis suggests the USD 4.8–4.9 Trillion (2025) cluster is the most defensible: it aligns with OECD price-level data showing US hospital prices 60% above the 12-country average, and with US national health expenditure of ~USD 4.5 Trillion in 2025, of which hospital services are the largest component. The USD 15.8 Trillion projection likely folds in physician services and long-term care, while the 8.6% US CAGR appears to blend price inflation with volume rather than measuring real output growth.
Segmentation matters because growth rates diverge sharply within the same market — inpatient care grows at ~4% while hospital-at-home expands at 7.6%, and payer mix shifts are re-rating entire ownership categories.
| Parent segment | Children |
|---|---|
| By Service Type | Inpatient Care, Outpatient Care, Emergency Services, Home & Hospital-at-Home Care |
| By Ownership | Public/Government, Private Non-Profit, Private For-Profit |
| By Hospital Size | Under 200 Beds, 200–499 Beds, 500+ Beds, Micro-Hospitals |
| By Payer Type | Public Insurance, Private Insurance & Managed Care, Out-of-Pocket, Medicare Advantage |
| By Service Area | Cardiovascular, Cancer Care, Acute Care, Diagnostics & Imaging, Neurorehabilitation & Psychiatry, Obstetrics & Gynecology |
Callout: Inpatient care holds ~60% of revenue but only ~4% growth; the home-care and micro-hospital formats are the fastest-compounding sub-segments at 7.6% and 8.7% CAGR respectively.
North America leads the global hospital services market with roughly 36% of 2024–2025 revenue, driven by the world's highest hospital price levels, deep private-insurance penetration, and consolidated for-profit chains. Asia Pacific is the fastest-growing region, posting 7–8% CAGR on insurance expansion and capacity build-out.
| Region | Market Share (%) |
|---|---|
| North America | 0.36% |
| Europe | 0.24% |
| Asia-Pacific | 0.27% |
| Latin America | 0.07% |
| Middle East & Africa | 0.06% |
Geography tree:
| Region | Share |
|---|---|
| North America | 36% |
| Asia Pacific | 27% |
| Europe | 24% |
| Latin America | 7% |
| Middle East & Africa | 6% |
The divergence between North America's revenue share and Asia Pacific's growth rate is the single most important regional signal: capital allocation and reimbursement strategy must be split, not scaled globally.
Growth is being driven by chronic-disease prevalence and insurance expansion, while labour inflation and public-payer reimbursement pressure are the dominant restraints. The net balance still favours expansion, but margin capture is shifting from volume to cost-to-serve discipline.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Chronic multi-morbidity prevalence | Driver | High | Longer length of stay, higher per-encounter cost |
| Insurance coverage expansion (APAC) | Driver | High | Channels latent demand into formal hospital networks |
| Ageing populations | Driver | High | US inpatient days to rise ~9% by 2030 |
| Hospital-at-home & micro-hospitals | Driver | Medium | 30–40% of inpatient days deliverable at home |
| AI-enabled throughput optimisation | Driver | Medium | 10–15% operational cost reduction potential |
| Labour & supply-chain inflation | Restraint | High | Labour at 60% of budgets; wages +10.1% vs reimbursement |
| Public-payer reimbursement pressure | Restraint | High | Medicare/Medicaid rate caps compress for-profit margins |
| Clinician shortages & burnout | Restraint | High | Capacity constraints limit revenue capture |
| Cybersecurity disruption | Restraint | Medium | Service outages and remediation costs |
Key implication: The drivers are structural and multi-year; the restraints are acute but cyclical. Operators who lock in labour productivity and payer-mix management now will capture disproportionate margin when wage inflation normalises.
The market is highly fragmented, with no single operator exceeding low single-digit global share. Differentiation rests on scale in payer negotiation, geographic density, and service-line depth rather than on proprietary technology.
| Company | HQ | Primary model | Scale / positioning |
|---|---|---|---|
| HCA Healthcare | USA | For-profit acute care | Largest US for-profit system, ~180+ hospitals |
| Kaiser Permanente | USA | Integrated payer-provider | Captive insurance + hospital network |
| Ascension Health | USA | Non-profit system | Large multi-state non-profit network |
| Mayo Clinic | USA | Academic / destination | Premium referral and research brand |
| Fresenius Helios | Germany | For-profit European leader | Largest private European hospital operator |
| IHH Healthcare | Malaysia | Emerging-market for-profit | Pan-Asia network across Singapore, Malaysia, India, Turkey |
| Fortis Healthcare | India | For-profit APAC | Active M&A consolidator in India |
Analytical note: Private for-profit chains are growing at 6.8% CAGR versus ~4% for public systems — the consolidation premium is real, and it is being driven by payer bargaining power, not clinical differentiation.
Procurement decisions in hospital services hinge on four mission-critical criteria: payer-mix exposure, labour-cost structure, regulatory compliance burden, and digital infrastructure maturity. Buyers selecting hospital partners or service vendors should stress-test counterparties against reimbursement concentration — a system with >50% public-payer revenue faces structural margin compression as rate updates lag wage growth.
Switching costs are high and asymmetric. Clinical integration, EHR interoperability, and physician privileging create multi-year lock-in once a hospital services relationship is established, meaning diligence must be front-loaded rather than exercised at renewal. Regulatory compliance — accreditation, minimum quality standards, and price-transparency rules — imposes significant administrative overhead that disproportionately disadvantages sub-scale operators.
For operators, the critical decision is format: micro-hospitals and hospital-at-home models carry lower capital intensity and faster payback but require robust remote-monitoring infrastructure and payer waivers that remain legislatively uncertain. Building that optionality now is cheaper than retrofitting it after reimbursement rules settle.
The balance of evidence favours a constructive but selective outlook. The ~5% global CAGR is real and underpinned by demography and insurance expansion, but it masks a brutal margin bifurcation: revenue growth is broad, while profit growth is concentrating in operators with payer leverage, labour productivity, and format diversification. The strongest counter-argument is that hospital-at-home and micro-hospital formats could erode the inpatient revenue base faster than incumbents can redeploy capital — a genuine risk, but one that is currently constrained by legislative uncertainty and capital-cycle inertia.
Our analysis suggests the most under-priced variable in this market is payer mix, not service mix. Operators with rising Medicare Advantage and public-insurance exposure face a 6.9% volume growth offset by rate compression that most published forecasts do not model explicitly. This divergence implies that headline CAGR figures overstate the earnings growth available to undifferentiated providers.
Actionable strategy:
What would change our conclusion: A durable CMS waiver extension for Acute Hospital Care at Home, combined with public-payer rate increases exceeding wage growth for two consecutive years, would shift our position toward aggressive inpatient-capacity investment. Absent that, the selective stance holds.
While this overview frames the strategic picture, precise sub-segment forecasting by payer type, hospital size, and service line requires the full dataset and country-level modelling — the essential next step for execution-grade decisions.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 4.54% from 2020-2034 |
| Segmentation |
|
The global hospital services market was valued at approximately USD 4.3 Trillion in 2025, based on the consensus midpoint of published estimates. It is forecast to reach USD 5.8 Trillion by 2030, growing at a 5.2% CAGR.
North America leads with roughly 36% of global revenue, driven by the world's highest hospital price levels and deep private-insurance penetration. Asia Pacific is the fastest-growing region at 7–8% CAGR, fueled by insurance expansion and capacity build-out.
Hospital-at-home and home-care services are the fastest-growing segment at approximately 7.6% CAGR, followed by micro-hospitals at 8.7%. Inpatient care remains the largest segment but grows at only about 4% annually.
Leading operators include HCA Healthcare, Kaiser Permanente, Ascension Health, Mayo Clinic, Fresenius Helios, IHH Healthcare, and Fortis Healthcare. The market is highly fragmented, with no single operator holding more than low single-digit global share.
Growth is driven by rising chronic multi-morbidity prevalence, ageing populations, and rapid health-insurance expansion in emerging markets. Labour inflation and public-payer reimbursement pressure are the main restraints offsetting these drivers.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
This study applies a 70/30 primary-to-secondary research split. In-depth interviews were conducted with stakeholders across the hospital value chain, including hospital systems and operators, group purchasing organisations, clinical service outsourcers, medical-equipment suppliers, and private-equity healthcare investors. Decision-maker designations interviewed include Chief Financial Officers, VP of Procurement & Sourcing, Heads of Clinical Operations, and Commercial and Payer Strategy Leads, ensuring that volume, pricing, and reimbursement perspectives were captured simultaneously.
| Stakeholder Role | Interview Share (%) |
|---|---|
| CFOs & Finance Leads | 35% |
| Procurement & Sourcing Directors | 30% |
| Clinical Operations Heads | 25% |
| Payer & Commercial Strategy Leads | 10% |
| Company Type | Representation (%) |
|---|---|
| Hospital Systems & Operators | 45% |
| Group Purchasing Organizations | 25% |
| Clinical Service Outsourcers | 20% |
| Healthcare Investors & Advisors | 10% |
Findings were benchmarked against official multilateral and governmental databases, including OECD health expenditure and hospital price-level publications, WHO health accounts, US CMS National Health Expenditure data, Eurostat healthcare statistics, and UN Comtrade for medical goods flows. Corporate annual filings (10-K, 20-F, investor presentations), patent databases, and recognised non-profit technical standards bodies were used to validate capacity, pricing, and service-line claims.
Market sizing triangulates a Top-Down allocation from macroeconomic health expenditure and insurance pools against a Bottom-Up model built from hospital capacity, bed counts, service pricing, and payer utilisation. Divergences between the two approaches were reconciled against published price-level indices and reimbursement tariffs.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |