 Cancer Immunotherapy Market
: 2026 Global Size and Outlook
Updated On : Nov 17, 2026|Base Year : 2025|Pages : 250

Amit Mardhekar
Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Cancer Immunotherapy Market
Amit Mardhekar
Research Analyst

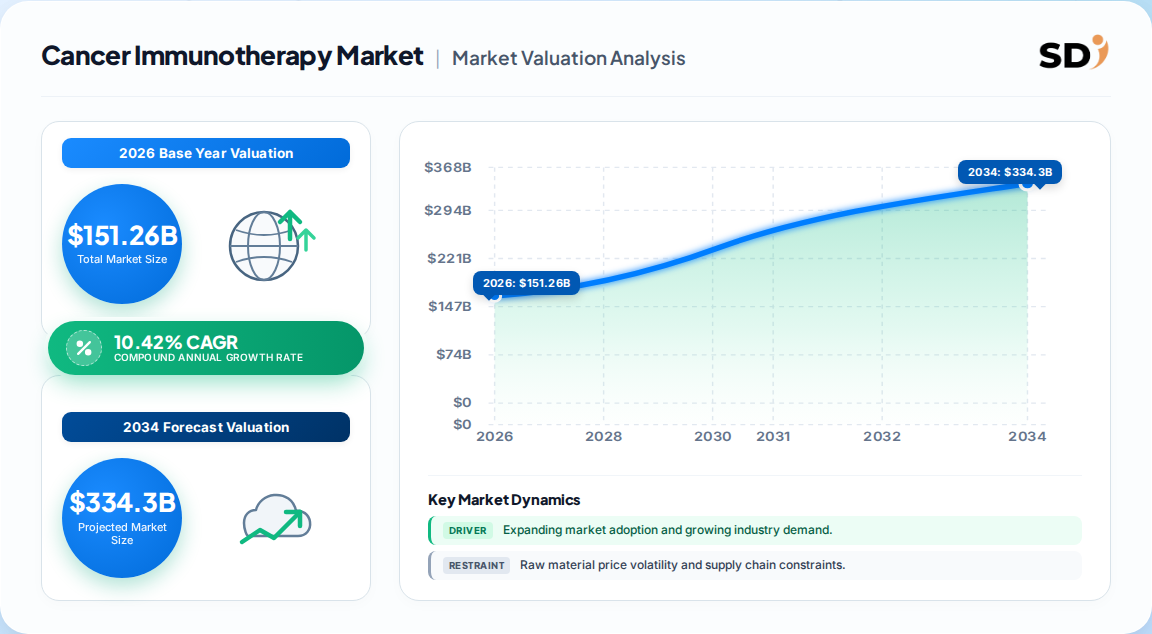
| Year | Market Size |
|---|---|
| 2025 | 136.4 B |
| 2026 | 151.3 B |
| 2027 | 167.0 B |
| 2028 | 184.3 B |
| 2029 | 203.5 B |
| 2030 | 224.7 B |
| 2031 | 248.0 B |

The cancer immunotherapy market encompasses therapeutic products that activate, modulate, or redirect the human immune system to identify and destroy malignant cells — including checkpoint inhibitors, monoclonal antibodies, adoptive cell therapies, cytokines, cancer vaccines, and oncolytic viruses — sold to hospitals, clinics, and research centers.
This report covers approved and commercially marketed immunotherapeutic products across major cancer indications, all delivery and distribution channels, and the five principal geographic regions. It analyzes revenue, volume, pricing, and pipeline dynamics. This analysis does not cover traditional chemotherapy, radiation therapy, small-molecule targeted kinase inhibitors, or standalone diagnostic imaging markets except where they directly intersect immunotherapy treatment pathways.
The global cancer immunotherapy market is most defensibly sized at approximately USD 151–166 billion in 2026, with forecast horizons diverging sharply depending on whether cell-therapy scaling and subcutaneous reformulation are modeled aggressively or conservatively. The table below compares the principal published estimates.
| Estimate (2026) | Base Year Value | Horizon Value | CAGR | Definition / Scope | Attribution |
|---|---|---|---|---|---|
| USD 151.26 Bn | USD 136.39 Bn (2025) | USD 367.63 Bn (2035) | 10.42% | Broad immunotherapy incl. mAbs, cell therapies, vaccines | One published estimate |
| USD 166.4 Bn | USD 153.3 Bn (2025) | USD 305.8 Bn (2033) | 9.0% | Product-segmented immunotherapy, hospital-weighted | A competing analysis |
| USD 144.2 Bn | USD 130.0 Bn (2023) | USD 247.2 Bn (2029) | 11.4% | Therapy-type segmented, checkpoint-inhibitor heavy | A competing analysis |
| USD 126.19 Bn (2023) | USD 126.19 Bn (2023) | USD 296.01 Bn (2033) | 8.9% | Broad immunotherapy, 2024–2033 horizon | A competing analysis |
Our analysis suggests the 10.42% CAGR path is the most defensible central case. It sits between the conservative 8.9% and the aggressive 11.4%, and it explicitly prices in the two structural forces now reshaping revenue: subcutaneous PD-(L)1 reformulation (e.g., FDA approval of Tecentriq Hybreza in September 2024) and the gradual manufacturing-cost decline in autologous CAR-T. The lower 8.9% figure likely underweights China-origin checkpoint inhibitors entering global tenders; the 11.4% figure likely overweights near-term cell-therapy capacity. The divergence itself is the insight: buyers should not anchor contracts to a single CAGR.
Product type, cancer indication, distribution channel, and end-user setting are the four non-geographic segmentation axes that matter commercially, with monoclonal antibodies and hospital settings dominating current revenue.
| Parent Segment | Children |
|---|---|
| By Product | Monoclonal Antibodies, Immunomodulators, Cancer Vaccines, Cell Therapies (CAR-T, TCR-T, TIL), Oncolytic Viruses, Cytokines |
| By Cancer Type | Lung Cancer, Breast Cancer, Melanoma, Leukemia, Lymphoma, Myeloma, Colorectal Cancer, Bladder Cancer, Others |
| By Distribution Channel | Hospital Pharmacy, Retail Pharmacy, Online Pharmacy, Specialty Pharmacy |
| By End User | Hospitals & Clinics, Cancer Research Centers, Specialty Clinics, Ambulatory Surgical Centers |
Monoclonal antibodies alone account for 61.6–71.5% of revenue depending on whether bispecific constructs are classified under mAbs or under cell-engagers. This classification choice is not academic: it shifts roughly USD 8–12 billion of 2026 revenue between segments and materially changes vendor rankings. Our analysis suggests buyers should insist on a normalized definition when comparing vendor share data, because the boundaries are inconsistent across published sources.
North America leads the global cancer immunotherapy market with approximately 43–45% of revenue, driven by early approval pathways, deep payer coverage, and concentration of cell-therapy manufacturing infrastructure in the United States.
| Region | Market Share (%) |
|---|---|
| North America | 0.43% |
| Europe | 0.25% |
| Asia-Pacific | 0.24% |
| Latin America | 0.04% |
| Middle East & Africa | 0.04% |
Asia Pacific's growth premium is real but uneven. Our analysis suggests the region's headline CAGR overstates near-term revenue because a large share of Chinese immunotherapy volume is domestically priced at 30–60% below Western list prices. The implication for Western vendors is that Asia Pacific growth will expand patient access faster than it expands global revenue — a critical distinction for anyone modeling regional P&L.
Rising global cancer incidence, a robust approval pipeline, and subcutaneous reformulation are the dominant growth drivers, while treatment cost and immune-related adverse events are the principal brakes on adoption velocity.
| Factor | Direction | Evidence Strength | Mechanism |
|---|---|---|---|
| Rising cancer incidence (47% growth 2020–2040 projected) | Driver | High | Expands eligible patient pool |
| Novel approvals (Imfinzi LS-SCLC, Amtagvi, ANKTIVA) | Driver | High | Opens new indications and lines of therapy |
| Subcutaneous PD-(L)1 reformulation | Driver | Medium-High | Cuts infusion time 7 vs 30–60 min; lifts throughput |
| Combination therapy research | Driver | Medium | Improves response rates, expands label coverage |
| High treatment cost and manufacturing complexity | Restraint | High | Limits payer coverage and patient access |
| Immune-related adverse events | Restraint | Medium | Slows adoption in comorbid populations |
| Capital intensity of cell-therapy facilities | Restraint | High | Constrains supply scaling through 2028 |
| AI-enabled biomarker and mRNA design | Opportunity | Emerging | Compresses discovery cycles and personalization cost |
The balance currently favors growth, but the restraint side is underappreciated. Our analysis suggests manufacturing capacity — not clinical demand — will be the binding constraint on cell-therapy revenue through 2028. Vendors that lock in contract manufacturing capacity early will capture disproportionate share; those that do not will cede ground to vertically integrated competitors.
Merck, Bristol-Myers Squibb, Roche, AstraZeneca, and Johnson & Johnson anchor the competitive landscape, but cell-therapy specialists and Chinese biosimilar entrants are eroding incumbents' pricing power at the margin.
| Company | Core Immunotherapy Position | Strategic Moat |
|---|---|---|
| Merck & Co. | PD-1 leader (pembrolizumab franchise) | Installed base, broad label coverage |
| Bristol-Myers Squibb | Dual checkpoint + cell therapy | Combination IP, manufacturing scale |
| F. Hoffmann-La Roche | PD-L1 and bispecifics | Diagnostics-integrated companion testing |
| AstraZeneca | Imfinzi/Imjudo franchise | LS-SCLC first-mover, subcutaneous pipeline |
| Johnson & Johnson | BCMA CAR-T and bispecifics | Myeloma depth, global reach |
| Novartis | CAR-T pioneer | Approved product history, Kymriah data |
| Gilead (Kite) | Cell therapy | Yescarta/Tecartus label expansion |
Differentiation is shifting from molecule novelty to delivery economics. Our analysis suggests the moat of the next five years is not the target — it is the subcutaneous formulation, the manufacturing yield, and the payer contract. Vendors without at least two of these three will face margin compression even as revenue grows.
Procurement decisions in immunotherapy hinge on four mission-critical criteria: proven indication breadth, cold-chain and infusion logistics capability, reimbursement certainty, and pharmacovigilance maturity for immune-related adverse events. Switching costs are high and asymmetric — once a hospital formulary standardizes on a checkpoint inhibitor, the clinical training, adverse-event protocols, and payer prior-authorization workflows become embedded, making substitution slow even when a biosimilar or competitor is cheaper. Regulatory compliance is the second risk vector: FDA and EMA post-approval monitoring obligations, plus the EU's evolving HTA joint assessment framework, mean total cost of ownership extends well beyond unit price. Operators should also model the risk of channel shift — online and specialty pharmacy growing faster than hospital pharmacy — because it changes inventory, cold-chain, and patient-support economics. Finally, buyers should scrutinize whether a vendor's supply chain is single-sourced for any critical reagent; cell-therapy viral vectors remain a concentration risk that has already caused allocation delays in the sector.
The balance of evidence favors a 10–11% CAGR central case through 2035, but the strategic premium sits not in the headline number — it sits in the segment mix shift toward subcutaneous formats and allogeneic cell therapy. The strongest counter-argument is that cell-therapy manufacturing bottlenecks and payer pushback on six-figure price points could pull growth toward the 8.9% low case; we take that seriously but note that checkpoint-inhibitor revenue alone is large and sticky enough to hold the market above 9%. The divergence between published estimates is itself a buyer's signal: anyone presenting a single CAGR without a definitional footnote is selling certainty they do not have.
The evidence that would change our conclusion: a sustained decline in CAR-T manufacturing cost per patient below USD 40,000, or a major payer-led outcome-based contracting wave that resets price expectations across checkpoint inhibitors. Either would justify moving to the 11.4% high case and re-rating cell-therapy specialists upward.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 10.42% from 2020-2034 |
| Segmentation |
|
The global market is valued at approximately USD 151.26 billion in 2026, according to one published estimate, with a competing benchmark placing it at USD 166.4 billion. The spread reflects differing definitions of which cell therapies and bispecifics are included in the immunotherapy boundary.
Published CAGRs range from 8.9% to 11.4% over multi-year horizons. The most defensible central case is roughly 10.4% through 2035, balancing cell-therapy scaling against payer pressure on high list prices.
North America leads with approximately 43–45% of global revenue, supported by early approval pathways, deep payer coverage, and concentrated cell-therapy manufacturing. Asia Pacific is the fastest-growing region, led by China and Japan.
Monoclonal antibodies dominate with 61–72% of revenue depending on classification boundaries, followed by immunomodulators and cell therapies. Checkpoint inhibitors remain the single largest therapeutic sub-class by revenue.
Merck & Co., Bristol-Myers Squibb, F. Hoffmann-La Roche, AstraZeneca, and Johnson & Johnson lead the market, alongside cell-therapy specialists such as Novartis and Gilead. Chinese entrants are gaining share in domestic and emerging-market tenders.
High treatment cost, manufacturing complexity for autologous cell therapies, and immune-related adverse events are the main restraints. Payer coverage decisions and cold-chain logistics further slow adoption in price-sensitive and lower-income markets.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
This study applies a 70/30 primary-to-secondary research split. In-depth interviews were conducted across the immunotherapy value chain with biologic raw material and reagent suppliers, specialized cell-therapy producers, contract manufacturing and formulation partners, and global specialty distributors. Decision-maker designations included VP-level Sourcing, Heads of Oncology R&D, Technical Directors of Manufacturing, and Commercial Operations Leads. Interviews were structured to capture capacity, pricing, reimbursement, and pipeline timing data unavailable in public filings.
| Stakeholder Role | Interview Share (%) |
|---|---|
| Oncology R&D Heads | 35% |
| Procurement & Sourcing Leads | 30% |
| Technical Manufacturing Directors | 20% |
| Commercial Operations Leads | 15% |
| Company Type | Representation (%) |
|---|---|
| Biologic & Reagent Suppliers | 30% |
| Cell Therapy & Biologics Producers | 40% |
| Contract Manufacturing Organizations | 20% |
| Specialty Distributors | 10% |
Secondary validation draws on multilateral trade statistics (UN Comtrade, WTO), regional customs and pricing databases (US ITC, Eurostat), corporate annual filings and 10-K disclosures, patent databases (USPTO, EPO), and technical standards published by recognized industry and pharmacopoeial bodies. Regulatory approval records from the FDA and EMA were used to timestamp indication expansions and subcutaneous reformulations.
Sizing uses simultaneous Top-Down and Bottom-Up triangulation. Top-down modeling allocates macroeconomic oncology spend across indication and product segments; bottom-up modeling aggregates manufacturer capacity, realized net pricing, and end-user consumption by setting. Divergences between the two are reconciled against published clinical adoption rates and patient volumes.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |