Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.
Alpha 1 Antitrypsin Deficiency Disease Market by Disease Manifestation (Pulmonary AATD, AATD-Associated Liver Disease), by Treatment Setting (Infusion and Specialist Clinics, Home-Based Infusion, Transplant and Tertiary Centers), by Drug Class (Alpha-1 Proteinase Inhibitor, RNA Interference, RNA Editing, Gene Editing, Neutrophil Elastase Inhibitor), by Route of Administration (Intravenous, Subcutaneous, Inhalation, Oral), by North America (USA, Canada, Mexico), by Europe (Germany, France, United Kingdom, Italy, Spain), by Asia Pacific (Japan, China, Australia, South Korea), by Latin America (Brazil, Argentina), by Middle East & Africa (Saudi Arabia, South Africa) Forecast 2026-2034
Updated On : Nov 20, 2026|Base Year : 2025|Pages : 275
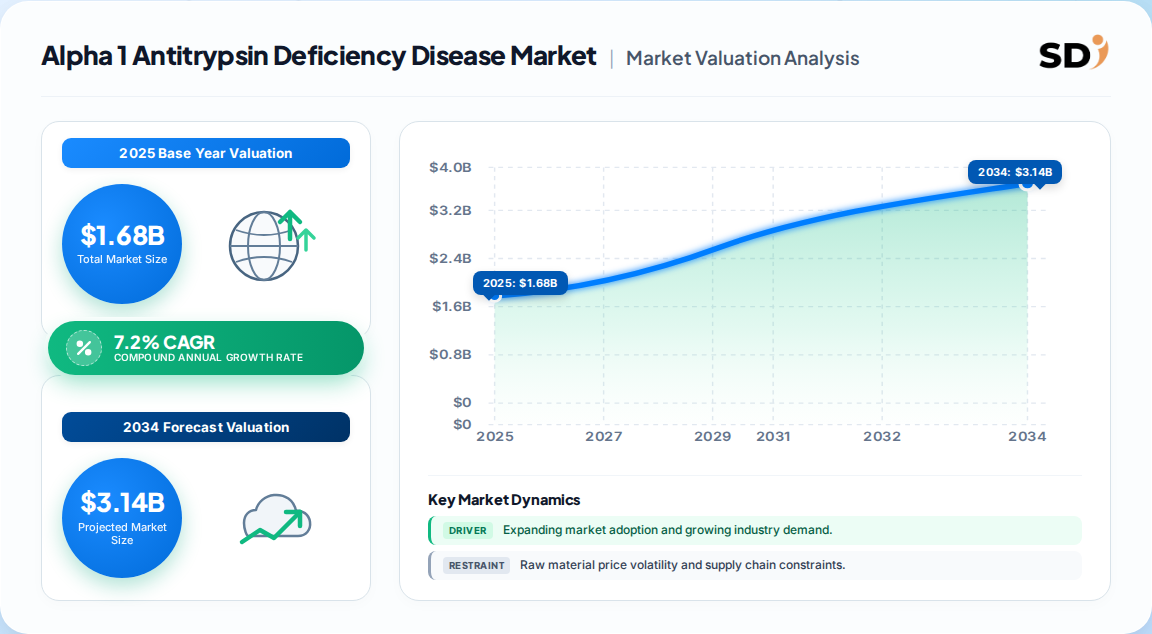
The global Alpha 1 Antitrypsin Deficiency Disease Market was valued at 1.68 Billion in 2025 across global markets, with the US alone representing roughly 780 Million.
The market is projected to reach 2.73 Billion by 2032, expanding at a 7.2% CAGR driven by late-stage RNA and gene-editing entrants.
Pulmonary AATD dominates with 82% revenue share; AATD-associated liver disease is the faster-growing segment at 10.7% CAGR.
North America leads with 60% share, followed by Europe at 26% and Asia-Pacific at 8%, where expansion is fastest.
Key players include Grifols (approximately 70% share), CSL Behring, Takeda, Kamada, Sanofi, Arrowhead, Beam, and Wave Life Sciences.
Why this matters for decision-makers: Incumbents reliant on weekly IV augmentation face margin compression as subcutaneous, RNA-editing, and one-time gene-correction therapies reset lifetime treatment economics before 2032.
Alpha 1 Antitrypsin Deficiency Disease Market Size (In Billion)
3.0B
2.0B
1.0B
0
1.680 B
2025
1.800 B
2026
1.930 B
2027
2.070 B
2028
2.220 B
2029
2.380 B
2030
2.550 B
2031
Alpha 1 Antitrypsin Deficiency Disease Market Size (In Billion)
Year
Market Size
2025
1.680 B
2026
1.800 B
2027
1.930 B
2028
2.070 B
2029
2.220 B
2030
2.380 B
2031
2.550 B
What is the Alpha 1 Antitrypsin Deficiency Disease Market?
The Alpha 1 Antitrypsin Deficiency Disease Market comprises therapeutics that restore or mimic alpha-1 antitrypsin (AAT) protein, reduce toxic mutant Z-AAT accumulation, or genetically correct the SERPINA1 defect. It spans plasma-derived augmentation therapy, recombinant AAT, RNA interference, RNA editing, and gene editing across pulmonary and hepatic manifestations.
Scope: what this report covers and excludes
This report covers the global therapeutic market for AATD across pulmonary and AATD-associated liver disease, segmented by drug class, route of administration, treatment setting, and geography. It includes marketed augmentation therapies and pipeline assets from Phase I through registration. This analysis does not cover COPD treatments unrelated to AATD, alpha-1 testing diagnostics as a standalone market, or liver transplant services.
How big is the market for Alpha 1 Antitrypsin Deficiency Disease Market?
Multiple published estimates diverge sharply, largely because of differing definitions of the treatable population, inclusion of pipeline revenues, and geographic coverage.
Estimate
Base Year
Horizon
CAGR
Definition / Scope
Attribution
1.68 Billion
2025
2032
7.2%
Global; disease manifestation and treatment setting
One published analysis
3.53 Billion
2024
2035
13.23%
Global; drug type, route, distribution channel
A competing analysis
940 Million
2024
2036
~8% implied
7MM; augmentation plus emerging therapies
A third published estimate
4.4 Million
2024
2035
10.05%
7MM; likely unit or scope anomaly
A trade press release
The 1.68 Billion base is the most defensible. It aligns with Grifols' reported EUR 700–750 million Alpha-1 franchise and roughly 70% share, implying a global augmentation market near 1.0–1.1 Billion plusadjacent revenue. The 3.53 Billion figure likely bundles broader respiratory spending.
How is the market segmented?
The market segments primarily by disease manifestation, treatment setting, drug class, and route of administration, each carrying distinct commercial economics.
Parent Segment
Children
Disease Manifestation
Pulmonary AATD, AATD-Associated Liver Disease
Treatment Setting
Infusion and Specialist Clinics, Home-Based Infusion, Transplant and Tertiary Centers
Pulmonary AATD generated 1.38 Billion in 2025 (82% share), growing at 6.3%. Liver disease at 0.30 Billion grows faster at 10.7% because no approved disease-specific therapy exists, leaving fazirsiran as the potential first mover.
Which region leads in Alpha 1 Antitrypsin Deficiency Disease Market?
North America leads with 60% of global revenue in 2025, equal to 1.01 Billion, supported by four FDA-approved augmentation products and established specialty infusion infrastructure. Europe follows at 26%, with Asia-Pacific the fastest-growing region at 10.5% CAGR.
Our analysis suggests Europe's 26% share understates its genetic burden: the region holds roughly half the modeled PI*ZZ population, but NICE's terminated Respreeza appraisal shows reimbursement—not prevalence—governs conversion.
What is driving growth — and what is holding it back?
Diagnosis expansion and a maturing pipeline are the primary growth engines, while reimbursement restrictiveness and diagnostic delay constrain realized revenue.
Factor
Direction
Evidence Strength
Mechanism
Rising diagnosis and awareness
Driver
High
Screening programs uncover patients; Kamada's ex-US GLASSIA sales rose from 15.2 to 19.4 Million in 2025
Early-stage curative therapies
Driver
Medium
KB408 and BEAM-302 offer single-dose potential
Liver-directed RNAi
Driver
High
Fazirsiran Phase III could create a new revenue pool
Low diagnosis rate
Restraint
High
Fewer than ~10% of US PI*ZZ patients recognized
Restrictive payer criteria
Restraint
High
AAT thresholds, FEV1 limits, and emphysema confirmation gate access
Infusion burden and persistence
Restraint
Medium
Only 46.5% persisted on original therapy for 12 months
The balance favors growth, but conversion—not prevalence—is the binding constraint. Each newly diagnosed patient translates directly into recurring revenue, as Kamada's sales trajectory demonstrates.
Who are the leading vendors?
Grifols leads the augmentation market with roughly 70% share, followed by CSL Behring, Takeda, and Kamada in plasma-derived products, while Sanofi, Beam, and Wave lead disruptive modalities.
Company
Lead Asset
Modality
Differentiation
Grifols
Prolastin-C, Alpha1-PI 15%
Plasma-derived, subcutaneous
Scale, ~70% share, SWIFT-SC lifecycle extension
CSL Behring
Zemaira, Respreeza
Plasma-derived
RAPID CT-density evidence; European reimbursement friction
Takeda
Glassia, Fazirsiran
Plasma-derived, RNAi
Dual exposure to replacement and liver disease
Kamada
Glassia (manufacturing)
Plasma-derived, inhaled AAT
International growth; inhaled route potential
Sanofi
Efdoralprin alfa
Recombinant AAT-Fc
Three-to-four-week dosing interval
Beam Therapeutics
BEAM-302
In-vivo base editing
One-time correction across lung and liver
Wave Life Sciences
WVE-006
RNA editing
Reversible, monthly subcutaneous dosing
Incumbents compete on infusion infrastructure, payer relationships, and manufacturing scale. New entrants compete on treatment burden and disease modification, making brand switching less relevant than modality displacement.
What do buyers and operators need to know?
Procurement decisions hinge on total treatment economics rather than unit price. Weekly IV augmentation costs roughly 127,537 USD annually per user in historical claims data, with augmentation accounting for 75.3% of the cost differential versus non-users. Payers therefore apply tight eligibility criteria that gate conversion.
Operators must weigh site-of-care economics carefully. Clinics carry higher revenue intensity through specialist evaluation and monitoring, but home infusion is growing faster at 8.5% CAGR as patients prioritize flexibility. Persistence risk is material: only 46.5% of new users remained on their original therapy at 12 months.
Regulatory compliance varies by market. US payers require documented emphysema and AAT below 11 micromol/L; European access depends on national HTA outcomes, as NICE's terminated appraisal illustrates. Buyers evaluating pipeline assets should prioritize programs demonstrating functional AAT restoration, Z-AAT reduction, and durable outcomes—not pharmacokinetics alone.
Strategic Recommendations & Analyst Perspective
The balance of evidence favors a modality transition rather than simple market expansion. Through 2032, competition will unfold in three waves: improved augmentation (subcutaneous Alpha1-PI), RNA-based disease modification (fazirsiran, WVE-006), and genetic correction (BEAM-302, KB408). Each wave attacks a different cost center—convenience, liver pathology, and durability respectively.
The strongest counter-argument is that gene editing faces durability, safety, and reimbursement uncertainty, and that weekly augmentation's entrenched infrastructure will persist longer than disruption timelines suggest. Grifols' subcutaneous program and Sanofi's longer-interval recombinant could defend the replacement paradigm sufficiently to delay displacement.
Our analysis suggests the liver segment is the clearest near-term value creation opportunity. Fazirsiran's Phase III readout on histologic fibrosis would create a drug-treated market where none exists today, insulated from augmentation price competition.
Actionable strategy:
Investors should weight exposure toward liver-directed and RNA-editing programs, where incremental revenue pools form rather than share shifts occur.
Operators should build home-infusion and patient-support capabilities now, as persistence—not acquisition—drives lifetime value.
Vendors should prepare HTA dossiers emphasizing functional AAT and Z-AAT endpoints to satisfy increasingly restrictive payer frameworks.
What would change our conclusion: a failed fazirsiran Phase III, or BEAM-302 durability data showing waning M-AAT restoration, would reassert the replacement paradigm through 2032.
Table 14: Europe Alpha 1 Antitrypsin Deficiency Disease Market Revenue Billion Forecast, by Disease Manifestation 2020 & 2034
Frequently Asked Questions
1. What is the Alpha 1 Antitrypsin Deficiency Disease Market size in 2025?
The global market was valued at approximately 1.68 Billion in 2025, with North America accounting for 1.01 Billion. The US represents roughly 780 Million of global revenue, driven by four approved augmentation therapies.
2. What is the growth rate of the Alpha 1 Antitrypsin Deficiency Disease Market?
The market is projected to grow at a 7.2% CAGR from 2026 to 2032, reaching 2.73 Billion. Faster subsegments include AATD-associated liver disease at 10.7% and Asia-Pacific at 10.5%.
3. Which segment dominates the Alpha 1 Antitrypsin Deficiency Disease Market?
Pulmonary AATD dominates with 82% of 2025 revenue, equal to 1.38 Billion. Current augmentation therapy is primarily indicated for pulmonary disease with clinically evident emphysema.
4. Who are the leading companies in the Alpha 1 Antitrypsin Deficiency Disease Market?
Grifols leads with approximately 70% share through Prolastin-C. CSL Behring, Takeda, and Kamada follow in plasma-derived therapy, while Sanofi, Beam, and Wave Life Sciences lead emerging modalities.
5. What is driving growth in the Alpha 1 Antitrypsin Deficiency Disease Market?
Rising diagnosis rates, expanded genetic testing, and late-stage pipeline entrants drive growth. Fewer than 10% of US severe PI*ZZ patients are currently diagnosed, leaving substantial conversion headroom.
Research Methodology & Data Sources
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Primary Research & Industry Fieldwork
Our research methodology employs a 70/30 primary-to-secondary split, prioritizing direct industry engagement. We conducted in-depth interviews with stakeholders across the AATD therapeutics value chain, including plasma fractionation suppliers, specialized biologics producers, contract manufacturing organizations, and global specialty distributors. Interviews targeted decision-makers including VP of Sourcing, Heads of Clinical Development, Technical Directors, and Commercial Operations Leads, capturing perspectives on pricing, reimbursement, and pipeline timing.
Key Stakeholders Interviewed
Key Stakeholders Interviewed
Stakeholder Role
Interview Share (%)
Clinical Development & R&D Heads
35%
Procurement & Sourcing Directors
28%
Commercial Operations Leads
22%
Regulatory & Market Access Managers
15%
Industry Ecosystem Breakdown
Industry Ecosystem Breakdown
Company Type
Representation (%)
Plasma Fractionation & Biologics Producers
40%
Specialty Pharma & Biotech Developers
30%
Contract Manufacturing Organizations
18%
Global Specialty Distributors
12%
Secondary Benchmarking & Public Trade Validation
We triangulated findings against official multilateral trade databases (UN Comtrade, WTO, US ITC, Eurostat), corporate annual filings (10-K, SEC filings, investor presentations from Grifols, CSL Behring, Takeda, and Kamada), patent databases, and recognized rare-disease and respiratory associations including EURORDIS and the Alpha-1 Foundation.
Demand Modeling & Market Sizing Triangulation
We applied simultaneous Top-Down (macroeconomic allocation across respiratory and rare-disease segments) and Bottom-Up (manufacturer capacity, product pricing, and diagnosed-patient consumption modeling) triangulation to converge on defensible market estimates.
 Alpha 1 Antitrypsin Deficiency Disease Market