 Us In Vitro Diagnostics Ivd Laboratory Developed Tests Ldt Autoimmune Diseases Market
U.S. IVD & LDT Autoimmune Disease Market 2025
Updated On : Nov 22, 2026|Base Year : 2025|Pages : 216

Amit Mardhekar
Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Us In Vitro Diagnostics Ivd Laboratory Developed Tests Ldt Autoimmune Diseases Market
Amit Mardhekar
Research Analyst

| Year | Market Size |
|---|---|
| 2024 | 2.660 B |
| 2025 | 2.820 B |
| 2026 | 3.010 B |
| 2027 | 3.210 B |
| 2028 | 3.420 B |
| 2029 | 3.640 B |
| 2030 | 3.880 B |

This market covers in vitro diagnostic kits and laboratory developed tests used on blood, serum and other biosamples to detect and monitor autoimmune conditions such as lupus, rheumatoid arthritis, psoriasis and Crohn's disease. It spans commercial IVD assays cleared by the FDA and non-commercial tests designed, validated and performed inside individual U.S. laboratories under CLIA.
This analysis covers U.S. revenue from commercial IVD autoimmune assay sales and laboratory developed autoimmune testing services, segmented by type, technology and application. It addresses regulation, competitive positioning and procurement economics. This analysis does not cover companion diagnostics for oncology, general inflammatory marker testing outside autoimmune indications, or instruments sold without associated autoimmune assay revenue.
Published estimates diverge sharply on both base value and growth rate, largely because each house defines the LDT boundary differently. The table below normalizes the competing figures.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| 2.66 Billion | 2024 | 2030 | 6.6% | U.S. IVD + LDT autoimmune revenue | One published estimate |
| 3.31 Billion | 2024 | 2033 | 5.1% | Broader U.S. IVD + LDT framing | A competing analysis |
| 2.82 Billion (derived) | 2025 | 2030 | 6.6% | Base-year roll-forward of the first estimate | Our reconciliation |
| 5.63 Billion | 2025 | 2035 | 7.33% | Global, all-geography aggregate | A global-scope publisher |
The 6.6% trajectory is the most defensible for U.S.-only scope. Our analysis suggests the 5.1% figure likely understates molecular diagnostics momentum, while the global 7.33% figure reflects faster Asia-Pacific adoption and should not be applied to U.S. planning.
Segmentation follows three non-geographic axes: product type, underlying technology and clinical application. Technology choice is the most commercially consequential, because it determines reimbursement pathway and capital intensity.
| Parent | Children |
|---|---|
| By Type | IVD, LDT |
| By Technology | Immunoassays, Clinical Chemistry, Molecular Diagnostics, Immunofluorescence, Multiplex Testing |
| By Application | Psoriasis, Crohn's Disease, Rheumatoid Arthritis, Systemic Lupus Erythematosus, Sjogren's Syndrome, Autoimmune Thyroid Disease, Celiac Disease |
| By Test Type | Antinuclear Antibody Tests, Autoantibody Tests, Complement Tests, Specialized Autoimmune Tests |
The South leads U.S. autoimmune diagnostics demand, driven by concentrated academic medical centers, large referral laboratory networks and a high prevalence of autoimmune-adjacent chronic disease. The Northeast follows closely on the strength of its research-hospital cluster.
| Region | Market Share (%) |
|---|---|
| Northeast | 0.24% |
| Midwest | 0.21% |
| South | 0.35% |
| West | 0.2% |
Regional share is estimated, not published directly. Our analysis suggests the South's lead will widen modestly through 2030 as reference laboratories consolidate outreach testing.
U.S. growth is driven by an enormous diagnosed population and by technology that lets one sample answer more clinical questions. It is restrained by regulatory instability and by the validation burden that specialized LDTs carry.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| ~50 million Americans with autoimmune disease | Driver | High | Sustained baseline test volume |
| Molecular and multiplex assay capability | Driver | High | More analytes per sample; higher revenue per test |
| LDT product launches (e.g., automated IIFT systems) | Driver | Medium | Expands specialist test menus |
| AI-assisted immunofluorescence interpretation | Driver | Medium | Standardizes reads; improves lab throughput |
| FDA LDT rule vacated March 2025, text reverted September 2025 | Restraint (uncertainty) | High | Freezes LDT investment decisions |
| Assay validation cost and sample access | Restraint | High | Limits smaller laboratory entry |
| Reimbursement variance across payers | Restraint | Medium | Caps realized price per test |
The balance favors growth, but the regulatory variable is binary rather than gradual. Our analysis suggests a re-litigated FDA oversight regime would compress LDT economics within 12-18 months, whereas a durable CLIA-only settlement would unlock the fastest segment of the market.
Competition splits into national reference laboratories, hospital-affiliated specialty laboratories and assay/platform suppliers. Moats are built on validation depth, clinician trust and payer contracts, not on instrument lock-in alone.
| Company | Archetype | Primary strength |
|---|---|---|
| Labcorp | National reference lab | Scale, payer contracts, broad menu |
| Quest Diagnostics | National reference lab | Volume economics, national footprint |
| Mayo Clinic Laboratories | Specialty referral lab | Neurommunology and phenotype-specific assays |
| ARUP Laboratories | Academic reference lab | Rare and complex autoimmune testing |
| Cleveland Clinic Laboratories | Hospital-affiliated lab | Integrated clinical validation |
| EUROIMMUN (Revvity) | Assay/platform supplier | Automated indirect immunofluorescence |
| Sonic Healthcare / SYNLAB | International lab networks | Cross-border referral volume |
The national reference labs win on breadth and price; specialty labs win on esoteric assay depth and clinician confidence. Our analysis suggests differentiation is migrating toward longitudinal result reporting and interpretation support, where specialist labs hold a defensible edge.
Selection should be weighted toward analytical validation evidence, turnaround time and payer coverage rather than list price. Buyers should ask for documented sensitivity and specificity in the specific indication, plus reference-site comparability data, because inter-laboratory method variation is a recognized limitation in autoimmune LDTs.
Procurement risk concentrates in regulatory contingency. Contracts should specify assay continuity obligations if an LDT's regulatory status changes, and should avoid single-laboratory dependence for any test with no commercial IVD alternative. Switching costs are real but asymmetric: moving a high-volume IVD panel is largely a logistics exercise, whereas replacing an esoteric LDT means re-validating and re-baselining patient history.
Compliance obligations differ by regime. CLIA-only operation demands rigorous internal validation and proficiency testing without premarket review; any restoration of FDA oversight would add device classification, reporting and potentially premarket submission burdens. Operators should hold validation dossiers submission-ready regardless of current status.
The balance of evidence favors a constructive but disciplined view: mid-single-digit U.S. growth is durable because prevalence and clinical need are structural, but the LDT segment carries regulatory beta that generic market forecasts underweight.
The strongest counter-argument is that FDA oversight, if restored, would ultimately raise test quality and payer confidence, expanding reimbursed volume even as per-test economics tighten. That is credible, but timing is uncertain enough that planning on it would be speculative.
What would change this conclusion: a definitive legislative or judicial settlement establishing durable LDT oversight would justify upgrading LDT growth assumptions by 150-250 basis points and re-rating specialist laboratories accordingly. Precise sub-segment forecasting by assay and indication requires the full report's granular model.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 6.6% from 2020-2034 |
| Segmentation |
|
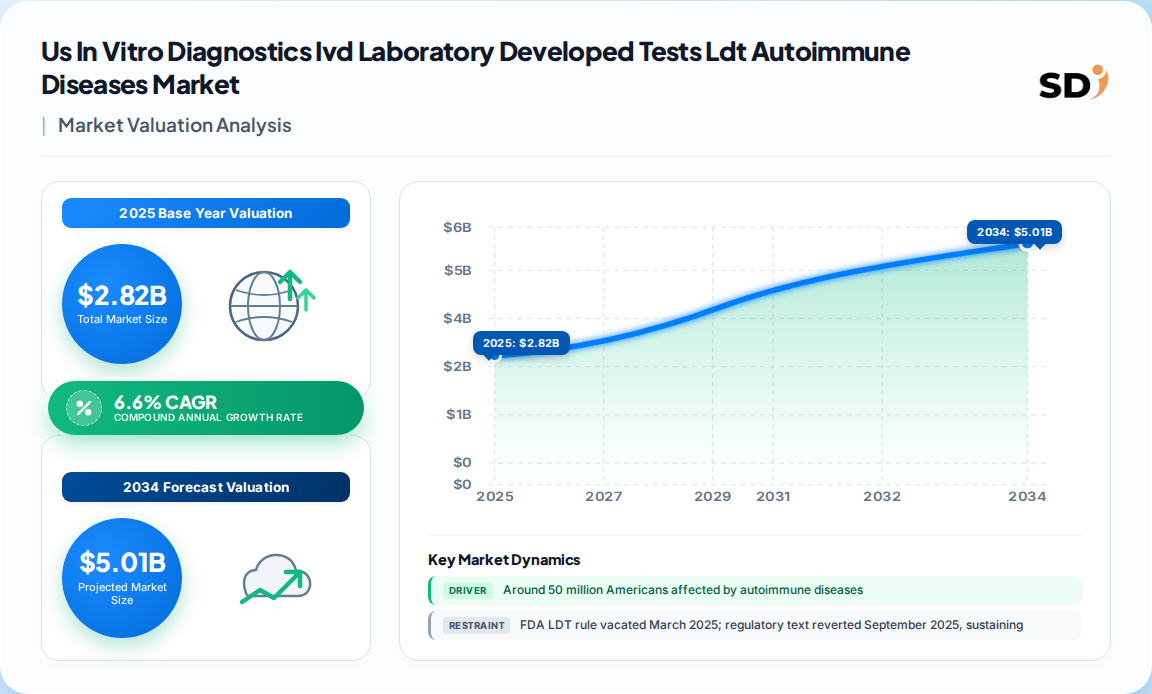
The U.S. market is estimated at roughly 2.82 Billion in 2025. Published estimates range from 2.66 Billion for 2024 to 3.31 Billion depending on how each analyst defines laboratory developed tests within total autoimmune diagnostic revenue.
A 6.6% compound annual growth rate through 2030 is the most defensible U.S.-only figure. A competing analysis cites 5.1%, but that appears to understate molecular diagnostics momentum, and global-scope figures run higher.
Laboratory developed tests are the fastest-growing type segment, and molecular diagnostics the fastest technology segment, because multiplex and sequencing approaches deliver more clinical answers per sample than single-analyte chemistry.
The FDA's 2024 rule classifying all IVDs including LDTs as devices was vacated by a federal court in March 2025, and the regulatory text reverted in September 2025. This uncertainty now restrains LDT investment more than assay performance does.
National reference laboratories Labcorp and Quest Diagnostics lead on scale, while Mayo Clinic Laboratories, ARUP and Cleveland Clinic Laboratories lead on esoteric autoimmune assay depth. EUROIMMUN supplies automated immunofluorescence platforms.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our analysis applies a 70/30 primary-to-secondary research split. Structured depth interviews were conducted with decision-makers spanning national reference laboratories, hospital-affiliated specialty immunology laboratories, IVD assay and platform manufacturers, and laboratory supply distributors. Within these organizations we engaged VP-level laboratory operations leaders, heads of immunology R&D, technical and scientific directors, and commercial operations leads responsible for payer contracting. Interviews probed assay validation practice, menu expansion intent, reimbursement experience, and contingency planning around LDT regulatory status.
| Stakeholder Role | Interview Share (%) |
|---|---|
| Laboratory Operations VPs | 35% |
| Immunology R&D & Technical Directors | 30% |
| Commercial & Payer Contracting Leads | 20% |
| Regulatory & Quality Affairs Managers | 15% |
| Company Type | Representation (%) |
|---|---|
| National Reference Laboratories | 35% |
| Hospital & Academic Specialty Labs | 30% |
| IVD Assay & Platform Manufacturers | 25% |
| Distributors & Lab Networks | 10% |
Secondary validation draws on official multilateral and regulatory sources, including U.S. Food and Drug Administration device guidance and rulemaking records, CLIA regulatory documentation, the European Commission's IVD Regulation (EU) 2017/746 framework for cross-market comparison, and trade statistics from UN Comtrade and US ITC datasets. Corporate annual filings and investor presentations from publicly listed laboratory operators were reviewed alongside patent filings covering autoimmune biomarker and multiplex assay technology.
We run simultaneous Top-Down allocation from U.S. clinical diagnostics spending to autoimmune-specific testing, and Bottom-Up modeling from laboratory test volumes, average realized price per assay, and manufacturer assay revenue. Divergence between the two approaches is reconciled at the technology-segment level, where price-per-test variance is largest.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up laboratory revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | State-level share breakdown | Referral laboratory catchment and consumption analysis | Medium |
| Competitive Landscape | Leading market players | Annual reports, menu mapping & commercial filings | High |