 In Vivo Cell Therapy Market
: Size, CAGR & 2035 Outlook
Updated On : Nov 22, 2026|Base Year : 2025|Pages : 272

Amit Mardhekar
Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 In Vivo Cell Therapy Market
Amit Mardhekar
Research Analyst

| Year | Market Size |
|---|---|
| 2024 | 16.89 B |
| 2025 | 17.85 B |
| 2026 | 22.28 B |
| 2027 | 27.80 B |
| 2028 | 34.70 B |
| 2029 | 43.30 B |
| 2030 | 54.04 B |

The in vivo cell therapy market covers therapies that reprogram a patient's immune cells directly inside the body — using lentiviral vectors, lipid nanoparticles, or oncolytic viruses — eliminating leukapheresis, ex vivo manufacturing, and lymphodepleting chemotherapy. It contrasts with ex vivo autologous models where cells are extracted, engineered in a GMP facility, and reinfused.
This analysis covers global in vivo delivery platforms across viral and non-viral vectors, target antigens, indications, and end-user settings, with revenue benchmarks drawn from both the broad cell and gene therapy delivery split and the in vivo CAR-T niche. This analysis does not cover ex vivo autologous or allogeneic manufacturing economics, small-molecule or protein therapeutics, or diagnostics.
Published estimates diverge sharply because definitions differ: broad in vivo delivery across all cell and gene therapies versus the narrow in vivo CAR-T platform segment. The table below isolates each basis.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| USD 16.89 billion | 2024 | 2034 | 18.7 (CGT total) | In vivo delivery method, all cell and gene therapies | One published estimate |
| USD 136.2 million | 2025 | 2036 | 32.2 | In vivo CAR-T only, trial-supply revenue | A competing analysis |
| USD 368.1 million | 2024 | 2034 | 61.5 | In vivo CAR-T potential, upside case | A competing analysis |
| USD 180.0 million | 2026 | 2036 | 32.2 | In vivo CAR-T, base case | A competing analysis |
Our analysis suggests the USD 16.89 billion 2024 in vivo delivery figure is the most defensible anchor for total market sizing, because it captures approved gene therapies delivered directly in vivo alongside emerging cell-reprogramming platforms. The CAR-T-only estimates describe a pre-revenue niche where the 61.5% upside case and the 32.2% base case differ by a factor of two — a spread that reflects approval-timing assumptions rather than demand disagreement. Buyers should treat the base case as planning-grade and the upside case as option value.
Segmentation splits along four non-geographic axes: delivery platform, target antigen, indication, and end-user setting. Platform choice is the single most consequential decision because it determines manufacturing footprint and dosing logistics.
| Parent segment | Children | 2026 share signal |
|---|---|---|
| By Delivery Platform | Viral vectors (lentiviral, AAV, retroviral), Lipid nanoparticles, Oncolytic viruses | Lentiviral 48.7% |
| By Target Antigen | CD19, BCMA, CD20, CD22, GPC3, HER2, Mesothelin, GD2 | CD19 34.8% |
| By Indication | Hematological cancers, Solid tumors, Non-oncology autoimmune | B-cell malignancies 28.7% |
| By End User | Specialty cancer centers, Hospitals, Academic institutes, Ambulatory infusion | Specialty centers 44.3% |
Lentiviral leadership is structural, not incidental: a single vial can write the CAR gene into T cells for durable expression without cell collection. Our analysis suggests the real contest is lentiviral versus lipid nanoparticle platforms — LNPs offer repeat dosing and simpler supply chains but shorter expression windows, making them better suited to autoimmune indications than to B-cell malignancies.
North America leads with roughly 48% of global in vivo cell therapy revenue, supported by concentrated CAR-T trial sites, fast-track FDA pathways, and specialist cancer centers capable of complex dosing. Asia Pacific is the fastest-growing region.
| Region | Market Share (%) |
|---|---|
| North America | 0.48% |
| Europe | 0.24% |
| Asia Pacific | 0.2% |
| Latin America | 0.04% |
| Middle East & Africa | 0.04% |
Our analysis identifies a second-order effect worth flagging: South Korea's approval of a domestically developed CAR-T product in 2026 creates an experienced clinical base that should accelerate local in vivo trial enrollment. Japan's comparatively low 24.7% CAGR implies regulatory conservatism, not weak demand — a distinction that matters for site-selection strategy.
Growth is driven by elimination of the leukapheresis-to-facility loop, which compresses treatment timelines and removes per-patient manufacturing slots. Restraints cluster around safety and specialist-dosing requirements.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| One-dose, off-the-shelf delivery | Growth | High | Removes cell collection, shipping, and lymphodepletion |
| Early efficacy data (4/5 responses; all 4 MRD-negative) | Growth | High | De-risks clinical programs and attracts sponsor funding |
| Large-pharma platform acquisitions (up to USD 14.35B) | Growth | High | Funds multi-site trials through late 2020s |
| Grade 3+ adverse events in early cohorts | Restraint | Medium | Keeps dosing inside specialist centers |
| Vector supply scarcity | Restraint | High | Caps enrollment and raises per-lot costs |
| Reimbursement uncertainty | Restraint | Medium | Delays commercial conversion post-approval |
The balance favors growth, but asymmetrically. Our analysis suggests safety data — not efficacy — is the binding constraint: platforms reporting no grade 3+ cytokine release syndrome will convert trial sites into commercial-ready centers faster than platforms with stronger response rates but heavier toxicity profiles.
Competitive position in 2026 is defined by platform ownership and clinical-stage proof rather than commercial revenue, since no in vivo product holds an approved label.
| Company | Platform focus | Distinguishing signal |
|---|---|---|
| Kelonia Therapeutics | Lentiviral, BCMA | Acquired by Eli Lilly up to USD 7.0B; all 4 patients MRD-negative |
| EsoBiotec (AstraZeneca) | Lentiviral | Single infusion responses in 4/5 myeloma patients; up to USD 1.0B |
| Capstan Therapeutics (AbbVie) | LNP, in vivo CAR-T | USD 2.1B acquisition; targeted LNP delivery |
| Interius BioTherapeutics (Kite) | Viral vector | USD 350M acquisition; targeted in vivo engineering |
| Orbital Therapeutics (BMS) | RNA/LNP | USD 1.5B acquisition; broader modality reach |
| Umoja Biopharma | CD19 viral | FDA Fast Track for UB-VV111, September 2025 |
| Vyriad | Oncolytic virus | Phase 1 VV169 at Mayo Clinic, up to 40 patients |
Differentiation rests on three moats: vector manufacturing yield, targeting specificity to T-cell subsets, and safety profile. Our analysis suggests the acquisition wave has already consolidated lentiviral leadership, leaving independent players to compete on non-viral delivery — a narrower but less contested lane.
For procurement leaders, the critical selection criteria are vector lot consistency, release-testing turnaround, and cold-chain integrity, since a single failed lot can halt an entire trial cohort. Switching costs are high: vector platform changes typically require comparability studies and regulatory re-filing, effectively locking sponsors into a supplier for a program's life.
Regulatory compliance varies by jurisdiction. The FDA's removal of REMS requirements for six autologous CAR-T products in 2025 lowered administrative barriers, but in vivo platforms will face fresh safety-monitoring conditions tied to insertional oncogenesis risk for integrating vectors. Operators should model two-week monitoring and specialist-center proximity into site contracts. Finally, buyers should verify GMP capacity reservations — not just supply agreements — because vector scarcity, not price, is the dominant procurement risk through 2030.
The balance of evidence favors a platform-consolidation thesis. Six acquisitions worth up to USD 14.35 billion were closed before any in vivo product reached approval, which means large pharma is buying optionality on a 16.3x revenue expansion rather than current cash flow. For suppliers and CDMOs, this signals that capacity contracts signed now will be repriced upward once first approvals land.
The strongest counter-argument is safety durability: if grade 3+ adverse events persist across larger cohorts, payers may restrict reimbursement to a narrow specialist network, capping addressable volume well below the upside case. We weight this risk as material but not thesis-breaking, because the platforms reporting clean cytokine profiles are the same ones attracting the largest acquisition premiums.
Actionable strategy for operators and investors:
What would change our conclusion: sustained grade 3+ toxicity across cohorts above 40 patients, or a regulatory delay pushing first approvals beyond 2030, would collapse the premium multiples underpinning current deal values. While this overview covers platform and regional economics, precise sub-segment forecasting requires program-level trial timelines and lot-level pricing.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
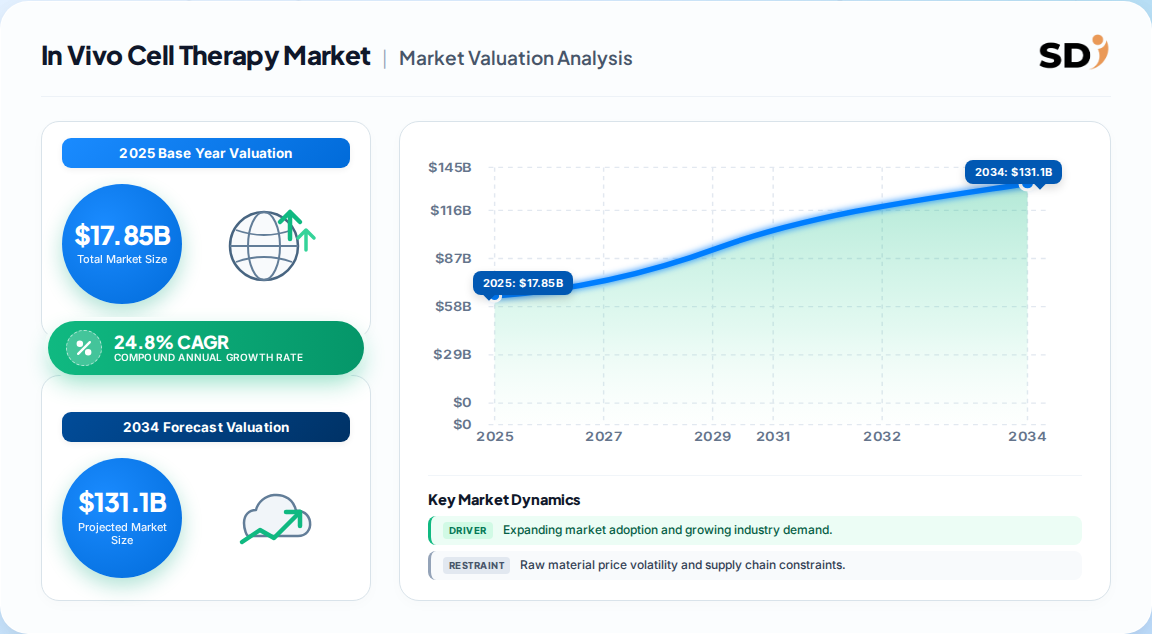
| Growth Rate | CAGR of 24.8% from 2020-2034 |
| Segmentation |
|
The broad in vivo delivery segment was valued at approximately USD 16.89 billion in 2024, with our synthesized 2025 base at USD 17.85 billion. The narrower in vivo CAR-T platform niche reached an estimated USD 180 million in 2026, reflecting its trial-supply stage.
Blended growth is approximately 24.8% through 2035 for in vivo delivery overall. The in vivo CAR-T sub-segment is forecast at 32.2% CAGR to 2036 in base case, with an upside case as high as 61.5% depending on approval timing.
North America leads with roughly 48% of global revenue, supported by concentrated trial sites and fast-track FDA pathways. South Korea (39.1% CAGR) and the USA (38.5% CAGR) are the fastest-growing profiled countries through 2036.
Lentiviral vector particles hold 48.7% of in vivo CAR-T demand in 2026, favored for durable CAR expression from a single dose. Lipid nanoparticles and oncolytic viruses are the principal challengers, with LNPs advantaged in repeat-dosing and autoimmune applications.
Kelonia Therapeutics (Eli Lilly), EsoBiotec (AstraZeneca), Capstan Therapeutics (AbbVie), Interius BioTherapeutics (Kite), Orbital Therapeutics (BMS), Umoja Biopharma, and Vyriad lead development. Six platform acquisitions since 2025 carry headline values up to USD 14.35 billion.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our analysis applies a 70/30 primary-to-secondary research split. In-depth interviews were conducted across the value chain: viral vector and plasmid suppliers, specialized cell-engineering producers, contract development and manufacturing organizations, and global distributors of cryopreserved therapy inputs. Decision-maker designations interviewed included VP-level sourcing executives, Heads of R&D, Technical Directors, and Commercial Operations Leads at sponsor companies and CDMOs.
| Stakeholder Role | Interview Share (%) |
|---|---|
| R&D & Technical Directors | 40% |
| Procurement & Sourcing Leads | 30% |
| Commercial Operations Leads | 18% |
| Regulatory Affairs Managers | 12% |
| Company Type | Representation (%) |
|---|---|
| Viral Vector & Plasmid Suppliers | 30% |
| CDMOs & Cell Engineering Producers | 40% |
| Distributors & Cryologistics Providers | 20% |
| Academic & Research Institutes | 10% |
We validated findings against official multilateral and regulatory databases, including UN Comtrade, WTO trade statistics, US ITC filings, and Eurostat pharmaceutical trade data. Corporate annual filings (10-K, SEC submissions, investor presentations), patent databases, and technical standards from recognized non-profit associations were used to corroborate platform and capacity claims. No third-party market research publications were used as validation sources.
We ran simultaneous Top-Down (macro healthcare allocation, therapy-class share, delivery-method split) and Bottom-Up (manufacturer vector capacity, per-lot pricing, end-user consumption modeling) triangulation. Divergences between the two approaches were reconciled using trial-enrollment volumes and disclosed deal values as external anchors.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |