 Asia Pacific Digital Health Market
 Size, Forecast & Trends
Updated On : Nov 18, 2026|Base Year : 2025|Pages : 221

Srinwanti Kar
Senior Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Asia Pacific Digital Health Market
Srinwanti Kar
Senior Research Analyst

| Year | Market Size |
|---|---|
| 2024 | 72.28 B |
| 2025 | 89.77 B |
| 2026 | 111.5 B |
| 2027 | 138.5 B |
| 2028 | 172.0 B |
| 2029 | 213.6 B |
| 2030 | 265.3 B |

The Asia Pacific digital health market is the revenue generated from technology-enabled healthcare delivered across the region — tele-healthcare, mHealth apps, medical wearables, EMR/EHR systems, healthcare analytics, and the software, hardware and services supporting them — sold to patients, providers, payers, employers and governments.
This analysis covers the Asia Pacific digital health market by technology (tele-healthcare, mHealth, wearables, EMR/EHR, analytics), component (software, hardware, services), application, end-use and country, from 2024 to 2033. This analysis does not cover traditional pharmaceutical manufacturing, in-vitro diagnostics revenue, pure hospital construction, or non-digital medical device sales.
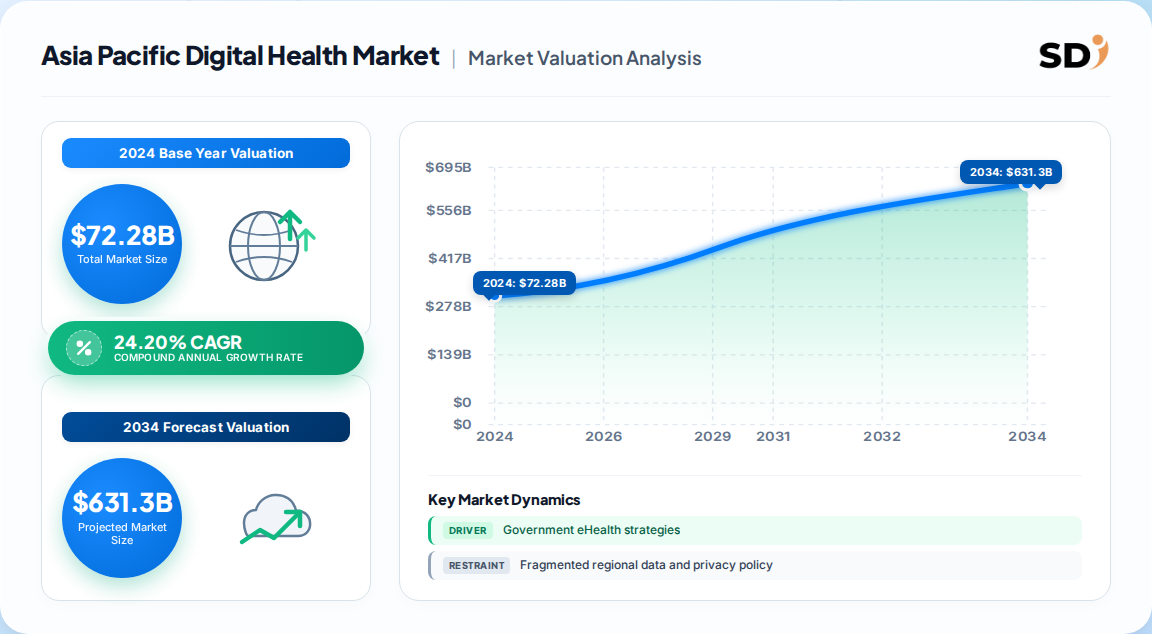
The Asia Pacific market was estimated at 72.28 Billion in 2024, with a projected 498.91 Billion by 2033 at a 24.20% CAGR; competing analyses cluster regional telehealth, wearables and mHealth into adjacent but narrower totals, so scope discipline matters when benchmarking.
Competing estimates for the Asia Pacific digital health market
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| 72.28 B → 498.91 B | 2024 | 2033 | 24.20% | Broad digital health: telehealth, mHealth, wearables, EMR/EHR, analytics, components | One published estimate |
| APAC telemedicine 105.77 B | — | 2030 | 18.4% | Telemedicine/virtual care only | A competing analysis |
| APAC wearables 7.5 B (2023) | 2023 | — | 28.4% | Wearable medical devices only | One published estimate |
| APAC mHealth apps 8.02 B (2023) → 23.01 B | 2023 | 2030 | 16.3% | Consumer mHealth applications only | A competing analysis |
| APAC healthcare AI 2.57 B (2024) → 100.07 B | 2024 | 2033 | ~50% | Clinical and administrative AI only | One published estimate |
Our analysis suggests the broad-estimate figure (24.20% CAGR) is the most defensible planning anchor, but it is an aggregate of sub-markets growing at very different rates. The wide dispersion — 16% for mHealth apps versus ~50% for healthcare AI — implies blended CAGR is a poor forecasting tool for individual product lines. Buyers should model sub-segment growth separately; this overview cannot substitute for segment-level forecasting.
Segmentation is technology-led, with tele-healthcare and mHealth driving volume, while services and software capture disproportionate value because integration, training and compliance work scales with adoption rather than replacing it.
| Parent segment | Children | 2024 share note |
|---|---|---|
| By Technology | Tele-healthcare, mHealth, Medical wearables, EMR/EHR systems, Healthcare analytics, Others | Tele-healthcare 44.98% |
| By Component | Software, Hardware, Services | Services 37.89% |
| By Application | Diabetes, Cardiovascular, Mental health, Oncology, Respiratory, Others | Diabetes 24.65% |
| By End-use | Patients, Providers, Payers, Employers, Others | Patients 34.47% |
The technology and component positions are reinforcing: tele-healthcare leads because it is the lowest-friction digital channel, and services lead components because deploying it demands workflow redesign, localisation and reimbursement navigation. Our analysis suggests the services share will hold or rise — a structural signal that value is migrating from licences to implementation and managed operations.
China dominates with the largest revenue share at 25.31% in 2024, followed by Japan and India; India is the fastest-accelerating major market on the back of national digital health infrastructure and a 39% projected CAGR in its broader health-tech ecosystem.
Connectivity underpins the ranking: APAC reached 1.5 billion mobile internet users in 2024, with 5G forecast to cover roughly half of mobile connections by 2030. This divergence implies China and Japan will drive near-term services revenue, while India and Southeast Asia drive volume growth — a split that matters for pricing strategy.
Growth is driven primarily by government digital health policy, chronic-disease burden, smartphone and 5G penetration, and post-pandemic acceptance of virtual care; it is restrained by fragmented data-regulation frameworks, uneven reimbursement, interoperability gaps and clinician adoption costs.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Government eHealth strategies and reimbursement reform | Driver | High | Codifies demand and de-risks vendor investment |
| Chronic disease burden (diabetes, CVD, cancer) | Driver | High | Sustains remote monitoring and mHealth demand |
| Smartphone/5G penetration | Driver | High | Lowers cost of delivery and enables video/RPM |
| Ageing populations | Driver | High | Expands long-term monitoring populations |
| Fragmented regional data and privacy policy | Restraint | Medium-High | Slows cross-border interoperability and RWD use |
| Uneven telehealth reimbursement | Restraint | Medium | Caps provider willingness to pay |
| Interoperability and EHR gaps | Restraint | Medium | Raises integration cost and services dependency |
The restraints are structural, not cyclical. Regional policy harmonisation — as pursued by industry consortia working on digital health data frameworks — is a slow-moving variable, so vendors should plan for country-by-country compliance rather than a unified regional rulebook. Notably, the restraint mix favours services-heavy business models.
Competitive leadership is fragmented across telehealth platforms, EHR/EMR incumbents, wearable and RPM device makers, and analytics providers; no single vendor holds region-wide dominance, so advantage accrues to those with local reimbursement and interoperability depth.
| Company type | Strategic position | Differentiation / moat |
|---|---|---|
| Telehealth & virtual care platforms | Scale and channel reach | Reimbursement integration, local language, clinician networks |
| EMR/EHR incumbents | Installed base in hospitals | Switching costs, data gravity, workflow lock-in |
| Wearable & RPM device makers | Consumer and clinical hardware | Sensor IP, miniaturisation, battery and 5G integration |
| Health analytics & AI vendors | High growth, low base | Data access, model validation, regulatory clearance |
| Health-tech conglomerates | Cross-segment bundling | Capital, distribution, government relationships |
Our analysis suggests moats are domestic rather than global: an EHR incumbent's switching-cost advantage in one country rarely transfers. Acquisitions and strategic alliances — the pattern behind several recent regional launches — are therefore faster than organic entry for cross-border expansion.
Selection criteria are shifting from feature breadth to integration depth, reimbursement compatibility and data-governance credibility. Because most APAC markets regulate health data nationally rather than regionally, procurement should treat localisation, hosting and consent management as mandatory gates, not optional extras.
Switching costs are highest in EMR/EHR and RPM platforms, where clinical workflow and device fleets are entangled; they are lowest in consumer mHealth, where churn is structural. Procurement risk concentrates in pilot-to-scale transitions: government-funded pilots often lack a funded renewal path, so buyers should negotiate scalability and exit terms up front. Compliance risk is asymmetric — a single data-handling failure can invalidate a multi-country rollout. Operators should also budget for clinician training and change management, which is where services spend concentrates and where most deployment delays originate.
The balance of evidence favours a services-led, country-by-country strategy over a single regional platform play. The headline 24.20% CAGR is real but is a composite of markets diverging between 16% and 50% growth; treating APAC as one market misallocates capital. The strongest counter-argument is that China's dominance (25.31% share) and scale could justify concentrating resources in one market — but that concentrates regulatory and reimbursement exposure in a single policy regime.
Our judgment is that the durable margin pool sits in services and integration, not licences. Tele-healthcare's 44.98% share will attract price competition and commoditisation, compressing pure-software margins; meanwhile the 37.89% services share expands as interoperability gaps persist. Vendors that build reimbursement-ready deployment capability and validated clinical evidence will capture premium pricing. Buyers who anchor on features rather than integration economics will overpay.
Evidence that would change this conclusion: harmonised regional data-regulation and cross-border telehealth reimbursement appearing within the forecast horizon, or services share declining below 30% — either would shift advantage back toward platform-led models.
| Region | Market Share (%) |
|---|---|
| China | 0.25% |
| Japan | 0.18% |
| India | 0.16% |
| South Korea | 0.1% |
| Australia & New Zealand | 0.11% |
| Southeast Asia | 0.14% |
| Rest of Asia Pacific | 0.06% |
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 24.20% from 2020-2034 |
| Segmentation |
|
It was estimated at 72.28 Billion in 2024 and is projected to reach 498.91 Billion by 2033, growing at a 24.20% CAGR. This makes Asia Pacific the fastest-growing major regional digital health market globally over the forecast period.
China leads with the largest revenue share at 25.31% in 2024, supported by policy momentum and scale. Japan and India follow, with India the fastest-accelerating large market as national digital health infrastructure expands.
Tele-healthcare was the largest technology segment at 44.98% of 2024 revenue, ahead of mHealth, wearables, EMR/EHR and analytics. Its lead reflects low deployment friction and strong post-pandemic acceptance of virtual consultations.
Government eHealth strategies, chronic-disease burden, smartphone and 5G penetration, ageing populations and durable clinician acceptance of virtual care drive growth. Restraints include fragmented data regulation, uneven reimbursement and interoperability gaps across markets.
Patients held the largest end-use revenue share at 34.47% in 2024, ahead of providers and payers. This reflects consumer-led adoption of mHealth apps, wearables and remote monitoring rather than purely institutional procurement.
Risks concentrate in fragmented national data-governance rules, unfunded pilot-to-scale transitions, interoperability gaps and clinician adoption costs. Buyers should gate contracts on localisation, consent management and funded renewal terms before committing.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our research programme applies a 70/30 primary-to-secondary split, with the majority of evidence gathered directly from the value chain. Structured depth interviews were conducted with stakeholders across four company categories: telehealth and virtual care platform providers, EMR/EHR and health IT vendors, wearable and remote patient monitoring device manufacturers, and digital health services and systems integrators. Interview programmes targeted decision-makers including Chief Medical Information Officers, Heads of Digital Health Product, Reimbursement and Market Access Directors, and Commercial Operations Leads across China, Japan, India, South Korea, Australia and Southeast Asia.
| Stakeholder Role | Interview Share (%) |
|---|---|
| Digital Health & Product Heads | 35% |
| Reimbursement & Market Access Directors | 30% |
| CMIOs & Clinical Informatics Leads | 20% |
| Commercial Operations Leads | 15% |
| Company Type | Representation (%) |
|---|---|
| Telehealth & Virtual Care Platforms | 30% |
| EMR/EHR & Health IT Vendors | 28% |
| Wearable & RPM Device Makers | 24% |
| Digital Health Services & Integrators | 18% |
Every estimate is cross-validated against official multilateral and regulatory sources. We draw on OECD revenue and health statistical publications, national health ministry digital strategies, WHO and international diabetes and cancer epidemiology registries, GSMA connectivity data, and corporate annual filings and investor presentations from listed digital health vendors. Patent filings, interoperability standards (HL7 FHIR) and published regulatory guidance inform segment definitions and technology adoption curves. No third-party market research publisher data is used as a validation source.
Sizing runs two parallel tracks. Top-down modeling allocates regional healthcare expenditure and digital IT budgets by segment and country, adjusted for policy maturity. Bottom-up modeling aggregates vendor revenue, device shipment volumes, subscription pricing and end-use consumption across patient, provider and payer channels. Divergence between tracks is reconciled against reported vendor performance before any forecast is published.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |