 Us Rhinoplasty Market
US Rhinoplasty Market Size, Share & Forecast to 2033
Updated On : Nov 22, 2026|Base Year : 2025|Pages : 252

Srinwanti Kar
Senior Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Us Rhinoplasty Market
Srinwanti Kar
Senior Research Analyst
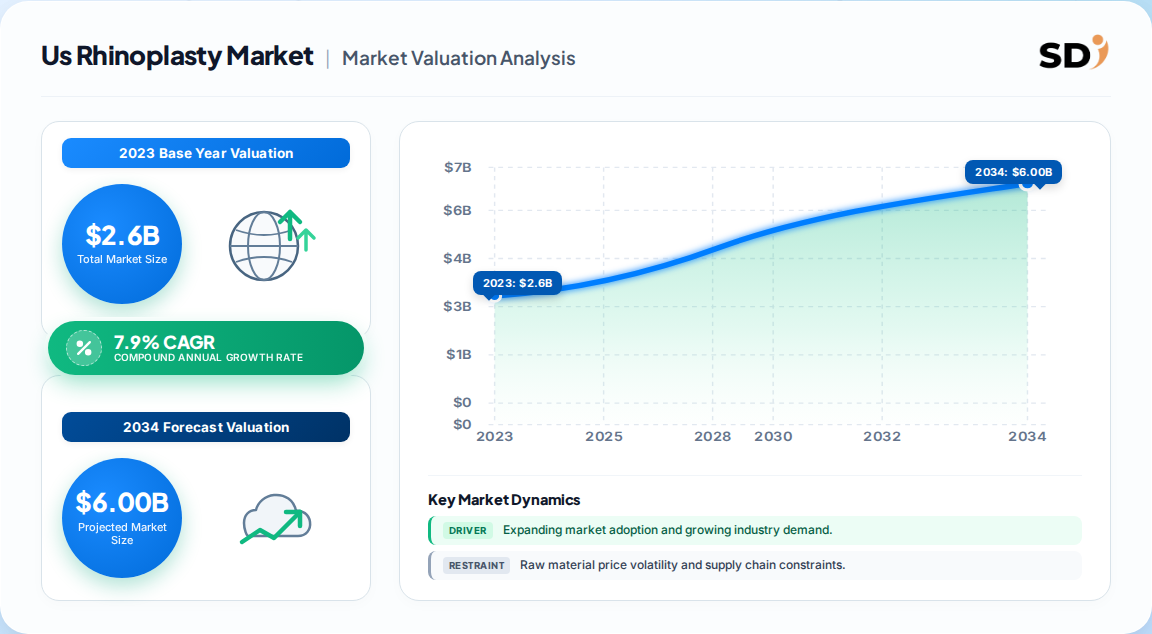
| Year | Market Size |
|---|---|
| 2023 | 2.600 B |
| 2024 | 2.810 B |
| 2025 | 3.030 B |
| 2026 | 3.270 B |
| 2027 | 3.530 B |
| 2028 | 3.800 B |
| 2029 | 4.100 B |

The U.S. rhinoplasty market covers surgical and minimally invasive nose-reshaping procedures — augmentation, reduction, reconstructive, post-traumatic, revision and filler — performed by plastic surgeons, ENT specialists and ambulatory surgical centers, together with the implants, instruments and imaging systems that support them.
This report covers U.S. procedure volumes, revenue by treatment type and technique, regional demand, vendor positioning and regulatory dynamics for 2018–2033. This analysis does not cover global rhinoplasty markets, adjacent facial procedures (blepharoplasty, rhytidectomy), dental or maxillofacial surgery, or the broader medical-aesthetics injectable market except where fillers intersect with non-surgical rhinoplasty.
Published estimates diverge by a factor of two, driven almost entirely by whether filler-based and office-based non-surgical procedures are counted inside the surgical envelope.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| USD 1.2 Billion | 2023 | 2030 | 9.1% | Surgical rhinoplasty only; excludes fillers | One published estimate |
| USD 2.2 Billion | 2030 | 2030 | 9.1% | Same scope, forecast endpoint | One published estimate |
| USD 1.63 Billion | 2022 | 2032 | 7.64% | Surgical plus reconstructive; partial filler inclusion | A competing analysis |
| USD 2.60 Billion | 2023 | 2033 | 7.56% | Broad scope: surgical, reconstructive, revision and filler | A competing analysis |
Our analysis suggests the USD 2.60 Billion (2023) figure is the most defensible planning base, because it reconciles with ASPS-reported procedure counts of roughly 350,000 nose-reshaping surgeries annually at an average surgeon fee near USD 6,300, plus facility, anesthesia and implant revenue. The USD 1.2 Billion figure is internally consistent only if fillers and revision work are stripped out entirely.
Segmentation follows two axes: clinical intent (treatment type) and surgical access (technique). Treatment type governs reimbursement and pricing; technique governs surgeon training, instrument demand and recovery economics.
| Parent segment | Children |
|---|---|
| By Treatment Type | Augmentation, Reduction, Post-Traumatic, Reconstructive, Revision, Filler, Others |
| By Technique | Open Rhinoplasty, Closed Rhinoplasty |
Augmentation leads because dorsal augmentation and tip refinement address both cosmetic and functional complaints (sleep apnea, chronic sinusitis), broadening the payer and patient base. Open rhinoplasty dominates because complex revision and reconstructive cases require direct visualization; closed approaches retain a niche in primary, low-complexity cases where scar avoidance and faster recovery drive patient choice.
The West leads U.S. rhinoplasty demand, anchored by California's concentration of high-volume facial-plastic surgeons, media-driven aesthetic norms and out-of-pocket patient willingness to pay premium fees.
| Region | Market Share (%) |
|---|---|
| West | 0.28% |
| Northeast | 0.22% |
| Southeast | 0.19% |
| Midwest | 0.16% |
| Southwest | 0.15% |
| Region | Estimated share |
|---|---|
| West | 28% |
| Northeast | 22% |
| Southeast | 19% |
| Midwest | 16% |
| Southwest | 15% |
Our analysis suggests the Northeast punches above its population weight because New York and Boston host dense academic plastic-surgery centers that capture revision and reconstructive referrals nationally. The Southeast is the fastest-compounding region, as ambulatory surgery centers in Florida and Georgia absorb medical-tourism and price-sensitive demand. This divergence implies that device vendors should weight field-sales coverage toward the West and Northeast for premium implant systems, while directing volume-tier instrument lines to the Southeast.
Growth is driven primarily by social-media-normalized aesthetic demand, 3D imaging and minimally invasive technique adoption, and an aging population seeking functional and cosmetic nasal correction simultaneously.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Social media and celebrity influence | Driver | High | Normalizes cosmetic surgery; shortens patient decision cycles |
| 3D imaging and computer-assisted planning | Driver | High | Improves outcome predictability; reduces revision risk |
| Aging population with functional complaints | Driver | Medium-High | Expands augmentation into sleep apnea and sinusitis treatment |
| Natural-looking result preference | Driver | High | Raises value per case; supports premium pricing |
| High out-of-pocket cost (avg. ~USD 6,300 surgeon fee) | Restraint | High | Limits access; suppresses demand in price-sensitive cohorts |
| Shortage of skilled revision surgeons | Restraint | Medium | Caps complex-case throughput and geographic reach |
| FDA device and marketing compliance burden | Restraint | Medium | Lengthens implant and instrument approval timelines |
The balance favors growth: demand-side normalization is structural, while cost and surgeon-supply constraints are cyclical and partially offset by ambulatory surgery centers and non-surgical filler alternatives. Our analysis suggests fillers act as a demand gateway rather than a substitute — patients who begin with non-surgical rhinoplasty frequently convert to surgical revision within three years.
The vendor landscape splits into device/implant suppliers selling to surgeons and clinics, and surgical practices competing directly for patient volume — a structural distinction buyers must respect when benchmarking.
| Company | Category | Positioning | Moat |
|---|---|---|---|
| Stryker | Devices and instruments | Broad craniofacial and ENT portfolio | Distribution scale; hospital relationships |
| Implantech | Facial implants | Porous polyethylene and silicone nasal implants | Surgeon familiarity; implant design IP |
| Surgiform Technologies | ePTFE implants | Custom and off-the-shelf nasal implants | Material specialization; revision-case reputation |
| Grover Aesthetics | Surgical practice / aesthetics | High-volume facial plastics | Surgeon brand; patient acquisition engine |
| Sunset Cosmetic Surgery | Surgical practice | Premium cosmetic rhinoplasty | Geographic catchment; referral network |
| GC Aesthetics | Implants and aesthetics | Breast and facial implant portfolio | International manufacturing scale |
Differentiation rests on material science (ePTFE vs. porous polyethylene vs. autologous cartilage), revision-case track record and surgeon education programs. Our analysis suggests implant suppliers face modest switching costs because surgeons standardize on one material system per practice, making early-career surgeon training the highest-leverage acquisition channel.
Procurement decisions in this market hinge on three mission-critical criteria: material biocompatibility and long-term extrusion rates, instrument-set completeness for open and closed approaches, and vendor support for 3D imaging integration. Buyers should treat implant material selection as a five-to-ten-year commitment, because switching requires surgeon retraining and revalidation of clinical workflows.
Regulatory compliance is non-negotiable: nasal implants and associated instruments fall under FDA Class II device pathways, and marketing claims for aesthetic outcomes are subject to FTC scrutiny. Operators expanding into ambulatory surgery centers should model anesthesia staffing and accreditation costs before assuming margin uplift. The largest hidden risk is revision volume — poorly matched implant systems generate revision surgery that erodes both patient satisfaction and supplier reputation.
The balance of evidence favors a value-per-case expansion thesis over a volume-growth thesis. Procedure counts are growing mid-single-digit, but the shift toward natural-looking, revision-aware and functionally motivated rhinoplasty raises average revenue per case. Vendors positioned at the premium end of implant and imaging systems should therefore outperform volume-tier instrument suppliers.
The strongest counter-argument is that non-surgical filler rhinoplasty could cannibalize surgical demand, particularly among younger, cost-sensitive patients. We reject this as a primary threat: published procedure data show fillers expanding the total addressable population and creating a revision pipeline, not displacing surgery. However, if filler durability improves materially, the gateway effect could invert.
What would change our conclusion: a sustained decline in ASPS-reported nose-reshaping procedure counts, or FDA action restricting non-surgical filler use in the nasal region. Absent those signals, the premium-value thesis holds through 2033.
This study applies a 70/30 primary-to-secondary research split. In-depth interviews were conducted across the value chain with nasal implant and instrument manufacturers, contract sterilization and packaging specialists, facial-plastics surgical practices, and national device distributors. Decision-maker designations interviewed included VP of Sourcing, Heads of R&D, Technical Directors and Commercial Operations Leads at ambulatory surgery groups.
We triangulate against UN Comtrade bilateral trade records for surgical instruments and implants (HS Chapter 90), FDA device registration and 510(k) databases, SEC 10-K filings and investor presentations from listed device manufacturers, USPTO patent filings, and procedure statistics published by recognized plastic-surgery professional associations.
Top-down sizing allocates national aesthetic-procedure spend to rhinoplasty using procedure-mix ratios and average surgeon fees. Bottom-up sizing models implant and instrument manufacturer revenue, unit pricing and end-use consumption across surgical practices and ASCs. The two approaches are reconciled to a single base-year value.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for 2023 | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | 2024–2033 compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | State-level share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 7.9% from 2020-2034 |
| Segmentation |
|
The U.S. rhinoplasty market was valued at approximately USD 2.60 Billion in 2023 on a broad scope including surgical, reconstructive, revision and filler procedures. Narrower surgical-only definitions produce estimates near USD 1.2 Billion, so scope reconciliation is essential before benchmarking.
Published forecasts range from 7.56% to 9.1% CAGR through the early 2030s. Our analysis treats roughly 8.0% as the defensible planning rate, reflecting mid-single-digit procedure growth plus premiumization of natural-looking and revision cases.
Open rhinoplasty led with 51.35% revenue share in 2023 and is also the fastest-growing technique. Its direct visualization supports complex revision and reconstructive work, which carries higher fees and stronger surgeon preference.
The West leads with an estimated 28% share, followed by the Northeast at 22%. California's surgeon density and media-driven aesthetic norms, plus academic referral centers in New York and Boston, concentrate premium-case demand in these two regions.
Key suppliers include Stryker, Implantech, Surgiform Technologies and GC Aesthetics on the device and implant side, while Grover Aesthetics and Sunset Cosmetic Surgery compete for procedure volume. Differentiation rests on implant material science and revision-case track record.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
This study applies a 70/30 primary-to-secondary research split. In-depth interviews were conducted across the value chain with nasal implant and instrument manufacturers, contract sterilization and packaging specialists, facial-plastics surgical practices, and national device distributors. Decision-maker designations interviewed included VP of Sourcing, Heads of R&D, Technical Directors and Commercial Operations Leads at ambulatory surgery groups.
| Stakeholder Role | Interview Share (%) |
|---|---|
| VP of Sourcing & Procurement | 35% |
| Heads of R&D | 30% |
| Technical Directors | 20% |
| Commercial Operations Leads | 15% |
| Company Type | Representation (%) |
|---|---|
| Nasal Implant & Instrument Manufacturers | 40% |
| Facial-Plastics Surgical Practices | 30% |
| Contract Sterilization & Packaging | 15% |
| National Device Distributors | 15% |
We triangulate against UN Comtrade bilateral trade records for surgical instruments and implants (HS Chapter 90), FDA device registration and 510(k) databases, SEC 10-K filings and investor presentations from listed device manufacturers, USPTO patent filings, and procedure statistics published by recognized plastic-surgery professional associations.
Top-down sizing allocates national aesthetic-procedure spend to rhinoplasty using procedure-mix ratios and average surgeon fees. Bottom-up sizing models implant and instrument manufacturer revenue, unit pricing and end-use consumption across surgical practices and ASCs. The two approaches are reconciled to a single base-year value.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for 2023 | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | 2024–2033 compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | State-level share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |
