 Corneal Pachymetry Market
 Outlook 2026
Updated On : Nov 19, 2026|Base Year : 2025|Pages : 240

Srinwanti Kar
Senior Research Analyst

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Corneal Pachymetry Market
Srinwanti Kar
Senior Research Analyst

| Year | Market Size |
|---|---|
| 2025 | 320.0 M |
| 2026 | 334.0 M |
| 2027 | 350.0 M |
| 2028 | 366.0 M |
| 2029 | 383.0 M |
| 2030 | 401.0 M |
| 2031 | 419.0 M |

Corneal pachymetry is the clinical measurement of corneal thickness, most often central corneal thickness (CCT), using ultrasonic or optical devices. It is a standard input to intraocular-pressure correction in glaucoma, pre-operative screening for refractive surgery, and keratoconus or ectasia detection, performed in hospitals, eye clinics and ambulatory surgical centers.
This analysis covers global corneal pachymetry devices and associated software across ultrasonic and optical modalities, four core applications (glaucoma diagnostics, refractive surgery planning, keratoconus and ectasia screening, and other corneal assessments), and the hospital, clinic and ambulatory-surgical-center end-user base. This analysis does not cover general ophthalmic diagnostic imaging platforms outside corneal thickness measurement, intraocular lens markets, surgical lasers, or contact-lens fitting services.
Published estimates diverge by nearly eight-fold, which is a segmentation problem before it is a forecasting problem — different publishers are counting different device populations. The table below places the leading figures side by side.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| USD 334.48 Million → 419.2 Million | 2026 | 2031 | 4.62% | Dedicated pachymetry devices, value terms | One published estimate |
| USD 305.14 Million → 435.44 Million | 2024 | 2032 | 4.5% | Pachymetry devices by product and end user | A competing analysis |
| USD 539.1 Million → 845.3 Million | 2024 | 2035 | 4.17% | Pachymetry devices, type and application | A competing analysis |
| USD 1.19 Billion → 2.5 Billion | 2024 | 2035 | 6.98% | Broad ophthalmic diagnostic framing | A competing analysis |
Our analysis suggests the USD 334.48 Million (2026) figure is the most defensible because its segment shares — 55.62% ultrasonic, 60.55% glaucoma, 38.21% North America — reconcile to a coherent installed-base story. The USD 1.19 Billion estimate almost certainly bundles combination ophthalmic imaging platforms; the USD 539.1 Million figure sits between device-only and platform-level counting. Buyers should treat the low-to-mid band as the device market and the high band as the adjacent diagnostic-suite market.
Segmentation is the clearest predictor of margin: modality determines price point and workflow fit, while application determines reimbursement and repeat-purchase frequency.
| Parent | Children | 2025 share | Growth signal |
|---|---|---|---|
| By Type | Ultrasonic method; Optical method | Ultrasonic 55.62% | Optical 6.89% CAGR |
| By Application | Glaucoma diagnostics; Refractive surgery planning; Keratoconus & ectasia screening; Others | Glaucoma 60.55% | Keratoconus 7.71% CAGR |
| By End User | Hospitals; Ophthalmology & optometry clinics; Ambulatory surgical centers | Hospitals 45.36% | ASCs 8.12% CAGR |
| By Modality | Handheld; Desktop / non-handheld | Handheld leads volume | Desktop fastest by capability |
Ultrasonic dominates on installed base and price, but optical coherence tomography and Scheimpflug systems are winning new placements because they eliminate contact, anesthesia risk and technician variability. That is why the fastest-growing application (keratoconus screening) is also the most optical-native — tomography, not ultrasound, detects early ectasia.
North America leads with 38.21% of 2025 revenue, but Asia-Pacific is the growth engine at 7.32% CAGR — the classic mature-versus-emerging split that should shape capital allocation.
| Region | Market Share (%) |
|---|---|
| North America | 0.36% |
| Europe | 0.24% |
| Asia-Pacific | 0.26% |
| South America | 0.07% |
| Middle East & Africa | 0.07% |
| Region | 2025 share | Growth outlook |
|---|---|---|
| North America | 38.21% | Mature, replacement-driven |
| Europe | 24% | Moderate, reimbursement-sensitive |
| Asia-Pacific | 26% | Fastest, 7.32% CAGR |
| Latin America | 7% | Infrastructure-led |
| Middle East & Africa | 7% | Early-stage, training-gated |
North America's lead rests on reimbursement when pachymetry accompanies tonometry, a dense specialist base and premium IOL economics. Asia-Pacific's advantage is volume: government-funded eye-hospital expansion, rising cataract and refractive case loads, and tele-ophthalmology programs that favor portable devices. Our analysis suggests APAC will not overtake North America on revenue before 2031, but it will determine which vendors win the next replacement cycle.
The balance of drivers favors expansion, but the two largest restraints are regulatory and reimbursement friction — both structural rather than cyclical, which caps the upside CAGR near 4.6–5.1% despite strong clinical demand.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Glaucoma and ocular hypertension prevalence | Driver +1.2% | High — OCTS-linked CCT risk data | CCT becomes routine risk stratification |
| Cataract and refractive surgery volumes | Driver +0.9% | High — APAC case growth | Mandatory pre-op thickness profiling |
| AS-OCT and Scheimpflug adoption | Driver +0.8% | Medium-high | Non-contact workflow, multipurpose ROI |
| Eye-care expansion in middle-income countries | Driver +0.7% | Medium | New clinics need portable screening |
| Tele-ophthalmology and handheld demand | Driver +0.5% | Medium | Rural and mobile screening |
| Inadequate reimbursement | Restraint −0.8% | High — payer variation | Pachymetry bundled or denied |
| Device and data-privacy regulation | Restraint −0.6% | High — FDA / EU MDR | Compliance cost and time-to-market |
| Platform interoperability gaps | Restraint −0.4% | Medium | Higher integration cost for buyers |
| Corneal-biomechanics substitutes | Restraint −0.3% | Emerging | Alternative diagnostics for ectasia risk |
The vendor field is medium-concentration, with a long tail of regional ultrasound specialists and a premium tier of optical and multimodal platform players. Differentiation now hinges on software, not optics alone.
| Company | Core modality strength | Positioning |
|---|---|---|
| Reichert Inc. | Ultrasound, tonometry integration | Installed-base leader, workflow bundling |
| Sonomed Escalon | Ultrasound pachymetry | Value-tier hospital and clinic footprint |
| DGH Technology | Dedicated ultrasound devices | Cost-efficient, high-volume screening |
| NIDEK Co. Ltd. | Optical and multimodal | Broad ophthalmic platform integration |
| Lumibird (Quantel Medical) | Optical, ultrasound | European specialist and export reach |
| Carl Zeiss Meditec | OCT and surgical planning | Premium non-contact, AI workflow |
| Topcon | Optical diagnostics | Integrated diagnostic suites |
| Tomey | Corneal topography and pachymetry | Keratoconus and screening niche |
Moats are built on three things: installed-base inertia in hospitals, integration with surgical planners such as premium IOL and refractive workflows, and reimbursement documentation support. Our analysis suggests the ultrasound incumbents' real risk is not technical obsolescence but pricing compression as optical systems move down-market into the same ASC and clinic accounts.
Selection should start with the clinical workflow, not the device. A glaucoma-heavy practice needs fast, repeatable CCT with reliable IOP-correction output; a refractive or keratoconus practice needs tomographic mapping, not a single thickness reading. Buying an ultrasound unit into a premium refractive setting is the most common avoidable capital error we see.
Procurement risk concentrates in three areas. First, reimbursement verification: payer rules vary materially, so model the pachymetry-denial rate before committing to per-procedure economics. Second, integration: check whether the device exports directly into the electronic medical record and surgical planner, because interoperability gaps create hidden labor cost. Third, regulatory status: confirm current FDA clearance or EU MDR certification, as compliance cost has lengthened upgrade cycles.
Switching costs are moderate and asymmetric. Replacing an ultrasound unit is straightforward and cheap; migrating a clinic off a multimodal optical platform that already holds topography, anterior-chamber and lens data is expensive in retraining and data continuity. Operators should therefore treat the initial optical purchase as a long-horizon platform decision, and negotiate software upgrade and service contracts at the point of sale.
The balance of evidence favors optical, non-contact platforms as the strategic high ground — but not the volume high ground. Ultrasonic devices will keep the majority of units for years because they are cheap, portable and adequate for screening, and that persistent demand is a legitimate business, not a legacy trap. The mistake would be to treat the 6.89% optical CAGR as a reason to abandon ultrasound servicing; the smarter play is a two-tier portfolio that defends the screening base while migrating premium accounts.
The strongest counter-argument is that platform consolidation, not modality shift, is the real threat: if buyers increasingly purchase thickness measurement as a feature of a multimodal diagnostic suite, standalone pachymetry vendors lose pricing power regardless of modality. We give this argument meaningful weight, because the ASC and premium-clinic growth is precisely where multimodal bundling is strongest — yet it does not change the direction of travel, only the speed.
What would change our conclusion: a step-change in corneal-biomechanics diagnostics that subsumes thickness measurement, or a reimbursement ruling in a major market that bundles pachymetry into a broader diagnostic payment — either would compress standalone device pricing faster than the current 4.62% trajectory implies. That is the scenario the full report stress-tests.
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 4.62% from 2020-2034 |
| Segmentation |
|
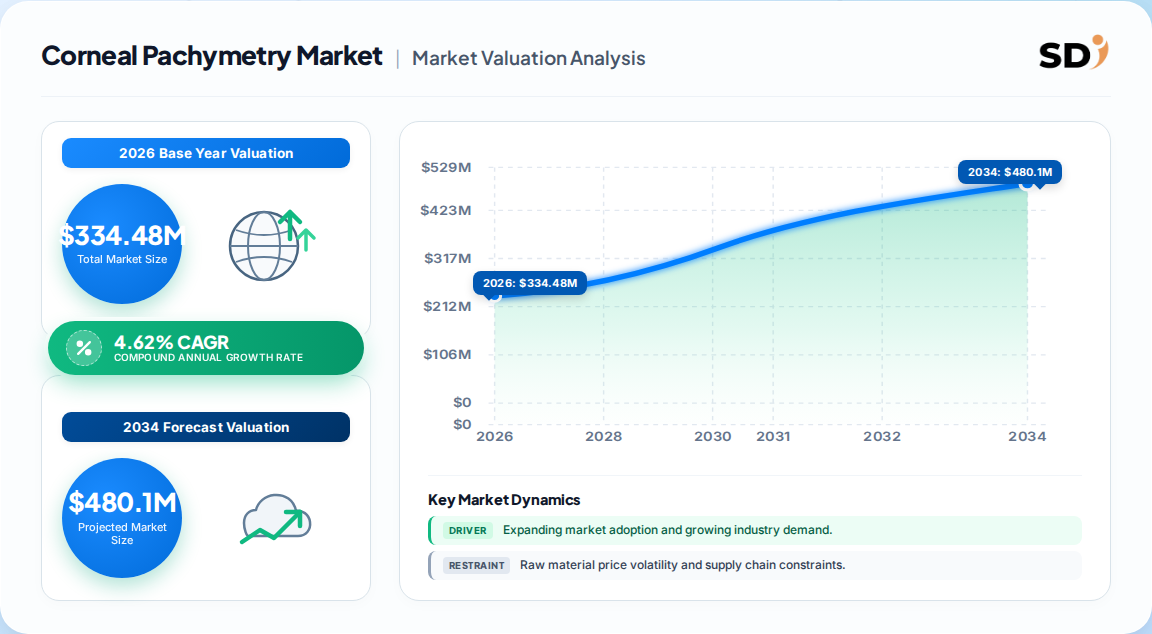
The global corneal pachymetry market is estimated at USD 334.48 Million in 2026, growing at a 4.62% CAGR to reach USD 419.2 Million by 2031. Some published estimates run higher where multimodal ophthalmic platforms are included in the count.
Ultrasonic pachymetry held 55.62% of 2025 revenue on installed base and price, but optical coherence tomography and Scheimpflug systems are growing at 6.89% CAGR as clinics shift to non-contact measurement.
Asia-Pacific is the fastest-growing region at 7.32% CAGR through 2031, driven by eye-hospital expansion, rising cataract and refractive volumes, and tele-ophthalmology programs. North America remains the largest at 38.21% of 2025 revenue.
Reichert, Sonomed Escalon, DGH Technology, NIDEK and Lumibird (Quantel Medical) are the major players, with Carl Zeiss Meditec and Topcon strong in optical and multimodal platforms. The market is moderately concentrated.
Central corneal thickness affects intraocular-pressure readings, and thinner corneas raise glaucoma conversion risk. Pachymetry is therefore used to correct IOP measurement and stratify risk, making it a standard glaucoma diagnostic input.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
Our research program applies a 70/30 primary-to-secondary split. Structured interviews were conducted across the value chain with optical component and transducer suppliers, dedicated pachymetry and multimodal ophthalmic device producers, software and integration partners, and global and regional distributors. Within these organizations we interviewed VP-level sourcing and procurement leads, heads of R&D and optical engineering, technical directors responsible for device validation, and commercial operations leads owning hospital and clinic accounts. Interview programs were weighted toward North America and Asia-Pacific to reflect where capital expenditure and reimbursement decisions concentrate.
| Stakeholder Role | Interview Share (%) |
|---|---|
| R&D & Optical Engineering Heads | 35% |
| Procurement & Sourcing Leads | 30% |
| Commercial Operations Leads | 20% |
| Regulatory Affairs Managers | 15% |
| Company Type | Representation (%) |
|---|---|
| Ophthalmic Device Manufacturers | 45% |
| Optical & Component Suppliers | 25% |
| Distributors & Channel Partners | 20% |
| Clinics & Surgical Centers | 10% |
Findings were cross-checked against official multilateral trade and standards databases including UN Comtrade, WTO tariff schedules, US ITC data and Eurostat medical-device trade flows. Corporate annual filings and investor presentations from listed ophthalmic device manufacturers were reviewed for segment revenue and capacity signals. Patent databases were screened for anterior-segment OCT and Scheimpflug innovations, and recognized technical standards and professional associations in ophthalmology and medical-device safety were used to validate regulatory and performance assumptions.
We run simultaneous top-down and bottom-up models. The top-down model allocates macroeconomic healthcare expenditure and ophthalmic diagnostic budgets to the pachymetry category by region and care setting. The bottom-up model builds from manufacturer unit capacity, average selling prices by modality, and end-use consumption across hospitals, clinics and ambulatory surgical centers. Divergences between the two are reconciled at the segment level before any forecast is published.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production and revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis and demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis and regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping and commercial filings | High |