 Procalcitonin Testing Market
: Size, CAGR & 2033 Forecast
Updated On : Nov 17, 2026|Base Year : 2025|Pages : 188

Srinwanti Kar

Sector Data Insights (SDI) is a specialized market intelligence and strategic consulting firm focused on delivering high-quality, data-driven syndicated research reports, industry analysis, competitive intelligence, and advisory solutions. With a strong emphasis on analytical excellence, particularly in life sciences, analytical instrumentation, and related high-tech sectors, Sector Data Insights empowers manufacturers, investors, service providers, researchers, and decision-makers with actionable insights for strategic growth, innovation, and market leadership.
SDI combines deep domain expertise in laboratory and analytical technologies with advanced analytics to provide comprehensive market assessments, technology trend analysis, vendor share data, investment intelligence, supply chain insights, and forward-looking forecasts. Our research supports organizations navigating complex global markets across industries such as life sciences, semiconductors & electronics, consumer goods, materials & chemicals, construction & manufacturing, food & beverages, energy & power, automotive & transportation, ICT & media, aerospace & defense, and BFSI.

+1 2315155523
 Procalcitonin Testing Market
Srinwanti Kar
Senior Research Analyst

| Year | Market Size |
|---|---|
| 2025 | 309.0 M |
| 2026 | 328.0 M |
| 2027 | 351.0 M |
| 2028 | 375.0 M |
| 2029 | 401.0 M |
| 2030 | 429.0 M |
| 2031 | 459.0 M |

The procalcitonin testing market covers in-vitro diagnostic assays, reagents, instruments and software used to measure PCT concentrations in blood to support assessment of suspected bacterial infection, sepsis risk stratification and antibiotic stewardship decisions. It spans central-laboratory immunoassays and decentralised point-of-care formats across hospitals, clinics and urgent-care settings.
This analysis covers PCT assay reagents and consumables, instruments and analysers, and associated software and services across laboratory-based and point-of-care settings, segmented by technology, clinical application and end use, with a 2025 base year and forecasts to 2033. This analysis does not cover C-reactive protein (CRP), interleukin-6, presepsin or other sepsis biomarkers as primary markets, nor molecular bloodstream infection panels, blood-culture systems, or general clinical chemistry analysers sold without PCT capability. Veterinary PCT applications and transplant-monitoring use cases are noted only as emergent adjacencies.
Headline estimates cluster tightly around USD 310–353 million for 2025–2026, but long-horizon projections diverge by more than 70%, and that divergence is the single most important number a buyer must interrogate.
| Estimate | Base year | Horizon | CAGR | Definition / scope | Attribution |
|---|---|---|---|---|---|
| USD 309.4M → USD 519.5M | 2025 | 2033 | 6.8% | PCT testing reagents, instruments, software; lab + POC | One published estimate (Grand View-type scope) |
| USD 316.4M → USD 613.2M | 2025 | 2036 | 6.2% | PCT assay including test kits, serum-led sample scope | A competing analysis (FMI-type scope) |
| USD 291.9M → USD 915.3M | 2025 | 2034 | 13.54% | Procalcitonin antigen/antibody, CLIA/ELFA, research included | A competing analysis (broad antigen/antibody scope) |
| USD 328.6M → USD 664.8M | 2025 | 2035 | 7.30% | PCT testing, volume × reagent price plus instruments/software | A competing analysis (Precedence-type scope) |
Our analysis suggests the 6.2–7.3% band is the defensible range and the 13.54% figure is an outlier explained by scope inflation, not by demand: it bundles procalcitonin antigen and antibody reagent sales used in scientific research, which roughly doubles the addressable base and inflates the growth rate through a small-denominator effect. For procurement and investment planning, the ~7% consensus should be treated as the planning number, with upside optionality from point-of-care penetration rather than from price.
Revenue concentrates in four predictable places: reagents, the central laboratory, chemiluminescent immunoassay technology, and the hospital end user — each above 65% share, which tells buyers where negotiating leverage actually sits.
| Parent segment | Children | 2025 share |
|---|---|---|
| Product | Reagents & consumables; Instruments & analysers; Software & services | Reagents ~80% |
| Test setting | Laboratory-based testing; Point-of-care testing | Lab ~88% |
| Technology | Chemiluminescent & electrochemiluminescent immunoassays; Fluorescence immunoassays & immunochromatography; Others | CLIA/ECLIA ~66% |
| Clinical application | Sepsis & systemic bacterial infection assessment; Antibiotic stewardship & treatment monitoring; Others | Sepsis ~49% |
| End use | Hospitals; Clinics & urgent-care centres; Others | Hospitals ~70% |
| Sample type | Serum; Plasma; Whole blood | Serum ~34% |
The implication is structural: because reagents carry four-fifths of revenue and are consumed per test, competitive strategy is really installed-base strategy. Software & services is the smallest but fastest-growing product line as hospitals wire PCT results into sepsis alerts and stewardship dashboards — a margin-accretive wedge that instrument-only vendors cannot easily replicate.
North America leads with approximately 38.9% of 2025 revenue, followed by Europe at ~27.8% and Asia Pacific at ~26.4%; Asia Pacific is the fastest-growing region, with China identified as the highest-CAGR country market.
| Region | Market Share (%) |
|---|---|
| North America | 0.39% |
| Europe | 0.28% |
| Asia-Pacific | 0.26% |
| Latin America | 0.04% |
| Middle East & Africa | 0.03% |
| Region | 2025 share | Growth posture |
|---|---|---|
| North America | 38.9% | Mature, protocol-driven, reimbursement-constrained |
| Europe | 27.8% | Stewardship-led, price-sensitive tendering |
| Asia Pacific | 26.4% | Fastest growth; ICU capacity and assay availability |
| Latin America | ~4% | Emerging, distributor-led |
| Middle East & Africa | ~3% | Early-stage, tender-driven |
This divergence implies a two-speed market: Western revenue grows on serial testing and software attach, while Asia-Pacific revenue grows on first-time assay adoption. Vendors optimising a single global price architecture will under-serve one and over-charge the other.
The dominant driver is the clinical burden of sepsis — the WHO cites roughly 48.9 million cases and 11 million sepsis-related deaths annually — which makes early bacterial-infection assessment non-discretionary spending; the dominant restraint is analytical non-standardisation across assays.
| Factor | Direction | Evidence strength | Mechanism |
|---|---|---|---|
| Sepsis burden and early-diagnosis mandates | Driver | High | Protocolised, repeat PCT testing in ED/ICU |
| Antimicrobial stewardship and AMR | Driver | High | Guides antibiotic start/stop decisions |
| Automated assay availability on open analysers | Driver | High | Lowers lab adoption friction |
| Rapid / point-of-care formats | Driver | Medium-High | Cuts turnaround time in decentralised settings |
| Non-traceability to B·R·A·H·M·S standard | Restraint | Medium-High | Blocks cut-off comparability, slows platform switching |
| Non-infectious elevations (trauma, burns, surgery) | Restraint | Medium | Reduces standalone specificity |
| Renal dysfunction baseline distortion | Restraint | Medium | Complicates threshold application in CKD/dialysis |
| Reimbursement limits on serial testing | Restraint | Medium | Caps test frequency per episode |
| Post-market quality events and recalls | Restraint | Medium | Raises compliance cost, conservative procurement |
Our analysis suggests the balance favours growth, but the growth is volume-driven rather than price-driven. Because clinical algorithms depend on fixed PCT thresholds, standardisation is not merely a technical nuisance — it is an adoption brake that protects incumbent traceable assays and penalises new entrants. The 2025 analytical evidence that not all commercial assays are traceable to the B·R·A·H·M·S standard, together with FDA Class II recall activity in the category, implies that labs will pay a premium for comparability and post-market reliability documentation. That is a durable moat for the top five, and a real barrier for challengers.
The competitive core is concentrated among large immunoassay houses — Roche Diagnostics, Thermo Fisher Scientific, bioMérieux, Siemens Healthineers and Abbott — each leveraging installed analyser bases and traceable assay lineages.
| Company | Portfolio position | Primary moat |
|---|---|---|
| F. Hoffmann-La Roche | Full PCT franchise, broad analyser base | Brand, clinical evidence depth, installed base |
| Thermo Fisher Scientific | Assays and platform breadth | Reagent scale, distribution reach |
| bioMérieux | Sepsis and stewardship ecosystem | Clinical microbiology integration |
| Siemens Healthineers | Automated immunoassay menu | Hospital automation footprint |
| Abbott | Immunoassay and POC breadth | Point-of-care channel access |
| Danaher (Beckman Coulter) | Chemistry/immunoassay PCT | Open-analyzer pull-through |
| QuidelOrtho | Rapid and lab formats | Decentralised diagnostics reach |
| Fujirebio | Specialised immunoassay | Assay niche credibility |
| DiaSys | Procalcitonin FS (FDA 510(k), May 2025) | Open-chemistry compatibility, 10 µL / ~10-min assay |
| Shenzhen Mindray | Cost-competitive systems | Emerging-market price leadership |
Differentiation now runs on two axes: traceable analytical comparability (incumbents) and format accessibility (POC and open-chemistry challengers). The U.S. FDA 510(k) clearance of DiaSys Procalcitonin FS in May 2025, with a ~10-minute result and a 0.23–50 ng/mL range, is a concrete signal that the moat is being probed at the open-chemistry and speed frontier rather than at the brand frontier. This implies a slow erosion of reagent price premiums in mature lab markets even as total test volume climbs.
Selection criteria should be sequenced as traceability first, turnaround second, integration third, price fourth. A PCT assay not demonstrably traceable to the established standard forces each laboratory to locally revalidate clinical cut-offs, which transfers risk onto the buyer and adds months to deployment. Procurement teams should contract for calibration and control supply continuity, not merely kit price.
Switching costs are asymmetric. Moving a PCT assay between platforms requires method comparison, reference-interval verification and clinician re-education, so the real lock-in is workflow and evidence, not hardware. Operators should therefore treat instrument placement as a multi-year commitment and negotiate reagent pricing tiers with committed volume bands rather than list-price discounts. Regulatory compliance is manageable but unforgiving: Class II device status, corrective-action history and lot-to-lot calibration traceability should be audited before tender award, and buyers should insist on documented post-market surveillance responsiveness given observed recall activity in the category.
On the point-of-care side, buyers should validate that rapid PCT formats deliver actionable concordance with the laboratory method used for confirmatory testing, otherwise ED workflow gains are offset by downstream retesting. Clinics and urgent-care centres should model total cost per decision — including confirmatory tests — rather than per cartridge.
The balance of evidence favours a steady, volume-led ~7% CAGR rather than a step-change, and the single most defensible strategic position is ownership of the recurring reagent revenue attached to an installed analyser base. The 13.54% outlier should be discounted; it reflects a broader antigen/antibody scope, not faster underlying testing adoption.
The strongest counter-argument is that point-of-care could re-rate the market faster than the base case assumes. If rapid whole-blood PCT achieves convincing concordance and reimbursement in emergency and urgent-care settings, the centre of gravity shifts away from central laboratories and toward decentralised cartridge economics — compressing reagent revenue per test while expanding test counts, a mix shift that helps challengers and hurts incumbents. We regard this as a real but slower-moving risk, because standardisation and clinical-evidence requirements still gate adoption.
Actionable strategy for investors and operators:
What would change our conclusion: peer-reviewed outcome data showing limited incremental benefit of PCT-guided protocols in specific settings, or reimbursement denial for serial testing in a major market, would push the forecast toward the low end of the 6.2–6.8% band. Conversely, a validated, reimbursed rapid POC PCT with standardised traceability would justify the upper band and warrant a re-rating of decentralised formats.
This study applies a 70/30 primary-to-secondary research split. Structured depth interviews and a quantitative survey were fielded across the PCT value chain, spanning raw material and antibody suppliers, specialised assay reagent producers, contract manufacturers and formulators, global in-vitro diagnostic distributors, and hospital laboratory procurement groups. Interviewees were designated at decision-maker level, including VP-level Sourcing and Procurement, Heads of R&D and Assay Development, Technical Directors of Clinical Laboratories, and Commercial Operations Leads responsible for immunoassay portfolios. Interview instruments captured installed-base counts, reagent pricing per test, serial-testing frequency, tender terms and switching triggers, which were aggregated into regional demand curves.
Findings were cross-validated against official multilateral and national data sources, including UN Comtrade diagnostic reagent trade flows, WTO tariff schedules, US ITC and Eurostat healthcare and chemical trade statistics, and national statistical offices. Corporate annual filings (10-K and SEC submissions), investor presentations and regulatory databases — notably U.S. FDA 510(k) and recall records under 21 CFR 866.3215 — were used to reconcile product-level revenue. Patent databases and recognised technical standards, including ISO 15189 laboratory quality requirements and ISO 13485 device quality management, informed the adoption-barrier assessment.
Market sizing was produced through simultaneous top-down and bottom-up triangulation. The top-down pathway allocated macroeconomic healthcare expenditure and sepsis-related admission volumes by region to derive testable PCT demand envelopes. The bottom-up pathway aggregated manufacturer capacity, published reagent price points, test volumes per ED/ICU bed, and end-use consumption across hospitals, clinics and point-of-care settings, then reconciled both pathways against disclosed supplier revenue to produce the base-year estimate.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |
| Aspects | Details |
|---|---|
| Study Period | 2020-2034 |
| Base Year | 2025 |
| Estimated Year | 2026 |
| Forecast Period | 2026-2034 |
| Historical Period | 2020-2025 |
| Growth Rate | CAGR of 6.8% from 2020-2034 |
| Segmentation |
|
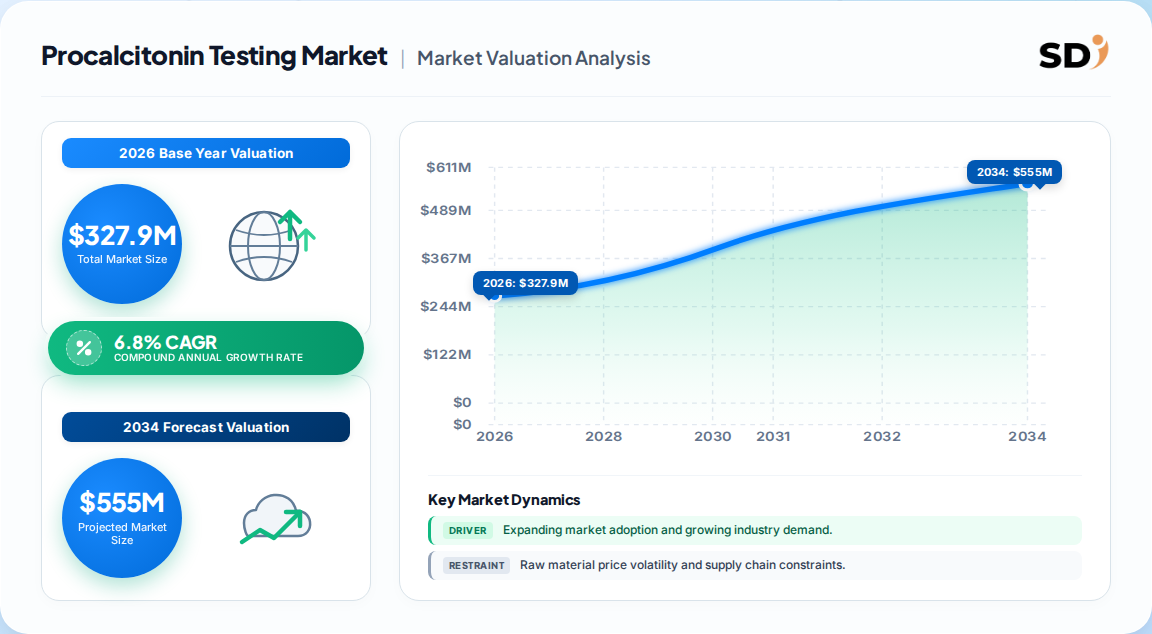
The global procalcitonin testing market is valued at approximately USD 327.9 million in 2026. Consensus projections place it at USD 519.5 million by 2033, representing a 6.8% CAGR, though broader antigen/antibody-inclusive definitions produce materially higher figures.
The dominant driver is the clinical burden of sepsis, estimated by the WHO at roughly 48.9 million cases and 11 million deaths annually. Antimicrobial stewardship programmes, automated assay availability and rapid point-of-care formats reinforce protocolised, repeat PCT testing in emergency and intensive-care pathways.
North America leads with approximately 38.9% of global revenue in 2025, supported by mature ICU infrastructure and sepsis protocol adoption. Asia Pacific is the fastest-growing region, driven by hospital capacity expansion in China and India.
Roche Diagnostics, Thermo Fisher Scientific, bioMérieux, Siemens Healthineers and Abbott form the competitive core. Danaher (Beckman Coulter), QuidelOrtho, Fujirebio, DiaSys and Shenzhen Mindray contest adjacent and emerging segments, competing on traceability, format accessibility and price.
Assay standardisation and result comparability are the primary restraints. Not all commercial assays are traceable to the established B·R·A·H·M·S standard, which complicates application of fixed clinical cut-offs, increases local validation burden and slows platform switching.
Our rigorous research methodology combines multi-layered approaches with comprehensive quality assurance, ensuring precision, accuracy, and reliability in every market analysis.
This study applies a 70/30 primary-to-secondary research split. Structured depth interviews and a quantitative survey were fielded across the PCT value chain, spanning raw material and antibody suppliers, specialised assay reagent producers, contract manufacturers and formulators, global in-vitro diagnostic distributors, and hospital laboratory procurement groups. Interviewees were designated at decision-maker level, including VP-level Sourcing and Procurement, Heads of R&D and Assay Development, Technical Directors of Clinical Laboratories, and Commercial Operations Leads responsible for immunoassay portfolios. Interview instruments captured installed-base counts, reagent pricing per test, serial-testing frequency, tender terms and switching triggers, which were aggregated into regional demand curves.
| Stakeholder Role | Interview Share (%) |
|---|---|
| R&D & Assay Development Heads | 38% |
| Procurement & Sourcing Leads | 32% |
| Commercial Operations Leads | 18% |
| Technical & Laboratory Directors | 12% |
| Company Type | Representation (%) |
|---|---|
| Assay Reagent & Antibody Producers | 42% |
| Instrument & Platform Manufacturers | 28% |
| Distributors & Hospital Procurement Groups | 20% |
| Contract Manufacturers & Formulators | 10% |
Findings were cross-validated against official multilateral and national data sources, including UN Comtrade diagnostic reagent trade flows, WTO tariff schedules, US ITC and Eurostat healthcare and chemical trade statistics, and national statistical offices. Corporate annual filings (10-K and SEC submissions), investor presentations and regulatory databases — notably U.S. FDA 510(k) and recall records under 21 CFR 866.3215 — were used to reconcile product-level revenue. Patent databases and recognised technical standards, including ISO 15189 laboratory quality requirements and ISO 13485 device quality management, informed the adoption-barrier assessment.
Market sizing was produced through simultaneous top-down and bottom-up triangulation. The top-down pathway allocated macroeconomic healthcare expenditure and sepsis-related admission volumes by region to derive testable PCT demand envelopes. The bottom-up pathway aggregated manufacturer capacity, published reagent price points, test volumes per ED/ICU bed, and end-use consumption across hospitals, clinics and point-of-care settings, then reconciled both pathways against disclosed supplier revenue to produce the base-year estimate.
| Dimension | Analytical Scope | Methodology Applied | Validation Level |
|---|---|---|---|
| Base-Year Market Size | Value in USD for base year | Bottom-up production & revenue triangulation | High |
| Forecast Horizon | Multi-year compound projection | Historical CAGR, regression analysis & demand elasticity | High |
| Regional Distribution | Regional share breakdown | Cross-border trade flow analysis & regional consumption | High |
| Competitive Landscape | Leading market players | Annual reports, capacity mapping & commercial filings | High |